What Is the Anion Gap?
The anion gap is a derived value that helps estimate the balance between measured positive and negatively charged electrolytes in the blood. It is commonly used as a screening tool in acid-base balance because it can point to hidden problems that may not be obvious from a basic lab result alone. The Anion Gap Calculator uses a few standard measurements from a blood test to generate this value https://anion-gap-app937.raidersfanteamshop.com/how-to-adjust-the-anion-gap-for-low-albumin rapidly and reliably.
In basic terms, the calculation compares sodium with chloride and bicarbonate. These are essential electrolytes found on many routine panels, including a serum chemistry panel. Because the body must keep these minerals in a narrow range, changes in their relationship can signal an underlying issue.
The anion gap does not directly measure every ion in the body. Instead, it calculates the difference between the major cations and anions that are directly reported. That is why it is useful as a diagnostic aid rather than a stand-alone diagnosis. It helps support interpretation, comparison, and medical review when values appear off the usual range.
How the Anion Gap Calculator Functions
An Anion Gap Calculator follows a typical formula using serum sodium, serum chloride, and serum bicarbonate. That equation is intended to estimate the difference between the listed cations and anions in the electrolyte panel. The result can help identify whether there may be an abnormal accumulation of acids or an unusual electrolyte imbalance.
The most common formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)Some clinicians use slight variations depending on the lab method or local reporting practices, but this basic version is the most familiar. The calculator is especially useful because it reduces manual calculation error and gives a fast, repeatable measurement from a standard serum chemistry panel.
The main inputs are:
- Serum sodium: the key positive electrolyte in the calculation Serum chloride: the principal negative electrolyte subtracted from sodium Serum bicarbonate: another important negative component included in the comparison
By bringing together these values, the calculator yields a number that can be compared with the expected reference range. That comparison supports interpretation of possible metabolic acidosis, compensation patterns, or other abnormalities in the lab result.
Sequential Calculation
Using the the calculator step by step is easy if you have the blood chemistry values in front of you. The main part is providing the correct measurement units and numbers exactly as reported.
Step 1: Locate the serum sodium value on the lab report. This is usually shown in milliequivalents per liter or a similar unit used in chemistry reporting.
Step 2: Locate the serum chloride value. This measurement reflects one of the main anions in the electrolyte panel.
Step 3: Locate the serum bicarbonate value, often listed as CO2 or total CO2 on a chemistry panel. This is the bicarbonate number used in the formula.
Step 4: Combine chloride and bicarbonate together. This produces the combined negative side of the calculation.
Step 5: Deduct that total from sodium.
Step 6: Check the result with the normal range or reference range used by the lab.
Here is a simple example of the calculation steps:
Sodium 140 − (Chloride 104 + Bicarbonate 24) = 12In this example, the anion gap is 12, which may be within a normal range depending on the laboratory’s method. The exact interpretation depends on the lab values, the units, and the clinical context. The calculator is best used as a fast calculation tool that supports, but does not replace, medical interpretation.
Standard Anion Gap Values and Why They Matter
The expected range for the anion gap can differ from a lab to another because of differences in analysis methods and equipment. That is why the reference range listed on the report matters more than a single universal number. A value that is normal for one lab may be a bit different at another.
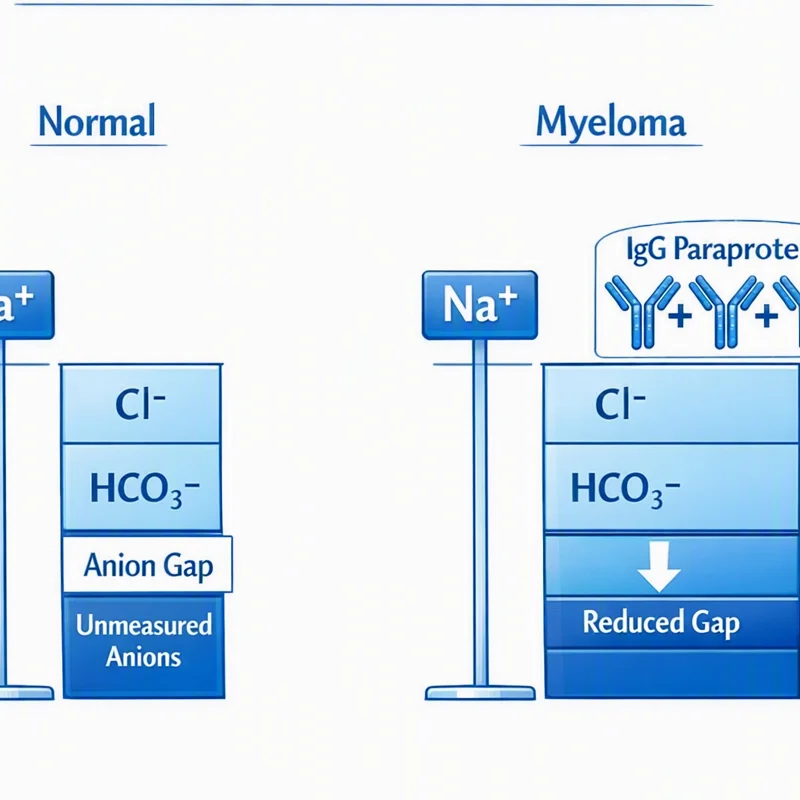
In general, a normal anion gap suggests that the measured electrolytes are in a balanced pattern. That does not automatically mean everything is normal, but it often means there is no obvious excess of unmeasured acids. A result outside the expected range may need additional review with other lab values and clinical information.
Albumin also matters because it is a major negatively charged protein in the blood. If albumin is low, the anion gap can appear decreased than expected even when there is an underlying problem. This is one reason why lab values should be interpreted with attention of protein status and overall health.
A useful way to think about the number is that it reflects a middle point in the blood’s chemistry. The calculation is not a diagnosis by itself, but it can help guide a broader assessment of acid-base balance and possible causes of an abnormal value.
Raised Anion Gap Compared with Decreased Anion Gap
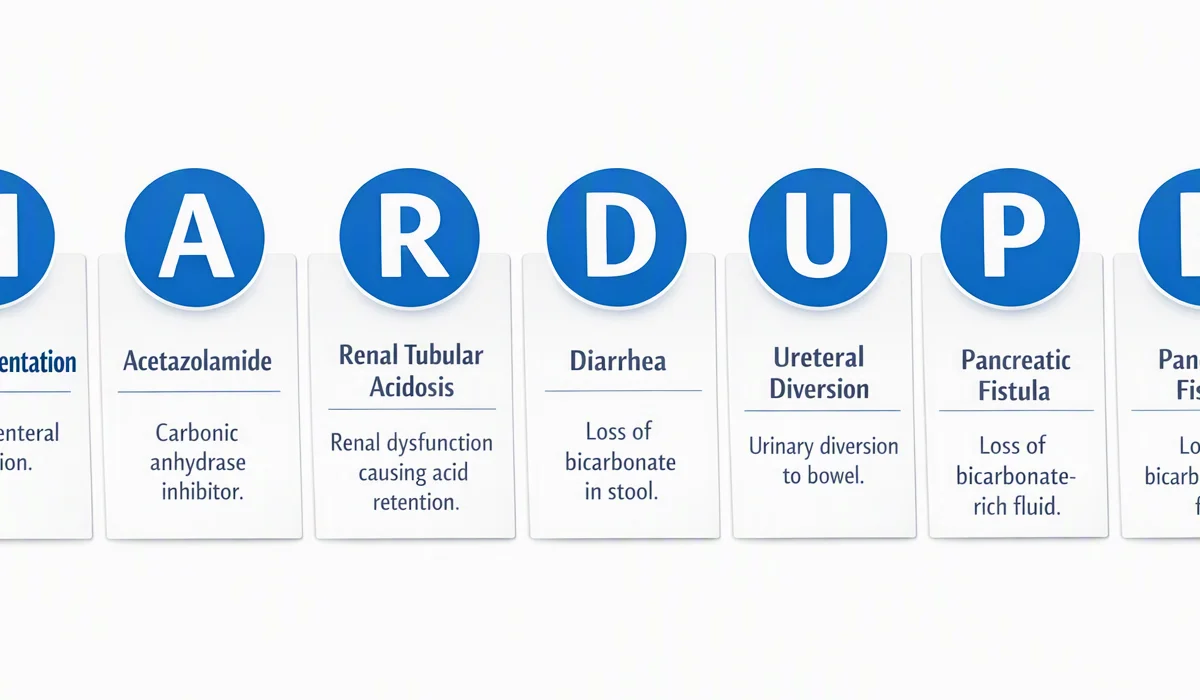
A elevated anion gap frequently indicates that more acids are found in the blood, which can be associated with metabolic acidosis. In such situations, the gap is widened because bicarbonate is being used up or replaced by unmeasured acids. This renders the calculation medically significant when evaluating an electrolyte imbalance.
A reduced anion gap is less common, but it can still be meaningful. It may occur because of low albumin, lab variation, or unusual changes in measured ions. Although less striking than a high result, a low gap can still require interpretation if it persists or appears with other abnormal findings.
The difference between the two is not just numerical. A high result often points toward acid accumulation, while a low result may imply a protein-related issue, a measurement problem, or a shift in electrolytes. The final significance depends on the blood test pattern, symptoms, and the rest of the chemistry panel.
Frequent Causes of an Unexpected Result
A number of conditions can cause an abnormal anion gap, especially when the value is high. A frequent cause is lactic acidosis, which happens when lactic acid rises faster than the body can clear it. This can occur in severe illness, poor oxygen supply, or other stress states.
Ketoacidosis is another important cause. In this condition, the body makes ketones as an alternate energy source, and these acids can elevate the gap. It is often discussed in relation to blood sugar disorders, but the core point is that excess acid shifts the calculation and suggests metabolic acidosis.
Kidney failure can also raise the anion gap because the kidneys are less able to eliminate acids efficiently. As acids collect, the gap may rise. This is why the result is often considered alongside other kidney-related lab findings.
Toxins may also change the gap. Certain intakes or contacts can create acids or interfere with normal chemistry patterns. In these situations, the anion gap can serve as an initial clue that calls for prompt medical review.
An abnormal value does not always has a dangerous cause, but any abnormal finding should be placed in clinical context. The same number can mean a different thing depending on symptoms, medications, hydration, and related blood test results.
How to Adjust the Anion Gap for Albumin
Because albumin holds negative electrical charge, a decreased albumin value can make the anion gap appear artificially low. This is why many clinicians use an albumin correction when reading the result. The aim is to calculate what the number would be if albumin were normal.
Low albumin, or hypoalbuminemia, can occur with illness, swelling, poor nutrition, liver problems, or protein loss. When albumin is diminished, the measured gap may underestimate the real acid-base disorder. A corrected anion gap can therefore deliver a more reliable picture.
The adjustment is usually done with a correction factor based on how far albumin is from the expected level. Different practices may use slightly different approaches, but the principle is the same: account for the contribution of protein to the acid-base balance.
This correction is especially important when the result appears within range or low but the patient still has signs of metabolic acidosis. In those situations, albumin correction can uncover a hidden abnormality that would otherwise be missed.
Drawbacks of the Calculator
Even a well-designed calculator has boundaries. One major issue is lab error, which can affect any blood test and alter the final number. A small mistake in one input may cause a misleading result, so it is always important to checking the source measurements before making conclusions.
Unit conversion is another typical concern. If values are entered in the wrong unit or copied from a report without understanding the reporting format, the result may be incorrect. The calculator depends on precise input and consistent units.
Measurement variability also matters. Different laboratories may use different instruments, methods, or reference intervals, which can affect the reported number slightly. This is one reason why comparison with the lab’s own reference range is more useful than relying on a single universal cutoff.
Most importantly, the result should always be interpreted in clinical context. The calculator is a useful diagnostic aid, but it cannot assess symptoms, medications, underlying illness, or the full pattern of electrolytes. A number alone cannot make a diagnosis.
When to Request Medical Interpretation
If an abnormal anion gap is found on a blood test, the next step is often a medical evaluation. This is especially true if the result is paired with symptoms or other concerning lab findings. The meaning of the number depends on the entire clinical picture, not just the calculation itself.
Symptoms such as confusion, severe weakness, shortness of breath, vomiting, dehydration, or sudden worsening illness may indicate that the abnormal value is clinically important. In these cases, prompt review can help determine whether the issue is related to metabolic acidosis, a toxin exposure, kidney failure, or another urgent problem.
Urgent care may be appropriate if symptoms are severe or if the abnormal result appears alongside unstable vital signs or major electrolyte abnormalities. Even when the calculator shows only a mild abnormal value, clinical significance can be high if the person is unwell.
If the result seems borderline or unexpected, the most appropriate next step is often a clinical review of the full panel, repeat testing when needed, and assessment of albumin, kidney function, and other related measurements.
Common Questions
How is the anion gap calculated?
The usual anion gap formula is: anion gap = sodium − (chloride + bicarbonate). This formula uses values from the serum chemistry panel and helps estimate the balance of measured electrolytes. Some laboratories use slightly different formulas, so it is important to check the result against the lab’s own method and reference range.
What is considered a normal anion gap?
A normal result depends on the laboratory’s normal values and reference range. Many labs report a range that reflects their specific measurement method. Due to this variation, the clearest interpretation is to compare the result with the range on the blood test report rather than relying on one universal cutoff.
Why would the anion gap be high?
A high anion gap often points to extra acids in the blood, which can happen with lactic acid buildup, ketone accumulation, kidney failure, or toxins. It can also indicate metabolic acidosis. The result should be considered alongside the rest of the electrolyte panel and the patient’s symptoms to determine the clinical significance.

What causes a low anion gap?
A low anion gap may happen with hypoalbuminemia, lab error, or other changes in measured electrolytes. Since albumin is a key negatively charged protein, low albumin can lower the gap even when the basic acid-base balance is not truly normal. You should also consider measurement variability and clinical context.
Is albumin correction needed for the anion gap?
Yes, correcting for albumin is often helpful when albumin is low or when the result does not match the clinical picture. A corrected anion gap can reveal abnormalities that a raw value might miss. This adjustment is particularly important in hypoalbuminemia because the protein level directly affects interpretation and overall acid-base balance.