What the Anion Gap Calculator Measures
An anion gap calculator is a useful diagnostic tool that estimates the difference between standard electrolytes in blood. The calculated anion gap helps providers judge electrolyte balance and focus the differential diagnosis of acid-base disorders, especially when evaluating metabolic acidosis.
The calculation relies mainly on sodium, chloride, and bicarbonate. These values come from routine lab values on a chemistry panel, and the result indicates the balance between measured ions and unmeasured ions or unmeasured anions in the blood. Because the body must maintain tight acid base balance, a change in the gap can signal a metabolic derangement that requires closer evaluation.
At https://ameblo.jp/anion-gap-lookup121/entry-12977392155.html a basic level, the anion gap is not a direct measurement of acid. Instead, it is a screening estimate that helps identify whether extra acids or other charged particles are present. A rising gap may indicate accumulation of acids, while a low gap can point to albumin changes, lab issues, or unusual cation excess. Used correctly, the calculator supports clinical assessment and more targeted interpretation of a patient’s chemistry profile.
In most settings, the calculator draws from serum sodium, serum chloride, and serum bicarbonate to support rapid bedside reasoning. That makes it especially useful when reviewing a serum chemistry panel in the context of acidemia, alkalemia, or a suspected compensatory response.
Formula for Anion Gap and Calculation Steps
The anion gap equation is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
This basic formula compares the main measured cation, sodium, with the major measured anions, chloride and bicarbonate. Some labs follow different conventions, but this is the most familiar version and the one many clinicians use for first review.
To use an anion gap calculator, start with the blood chemistry panel. Identify the sodium, chloride, and bicarbonate values. Then apply the equation one step at a time:
- Write down the sodium value. Combine the chloride and bicarbonate values together. Take away that sum from sodium. Assess the result with the lab’s reference interval.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the gap is 140 − (104 + 24) = 12. That result is often in a usual range, though the exact reference range depends on the lab.
The calculation is helpful because it turns routine electrolyte data into a clue about hidden acids or shifted ions. In a patient with suspected acidosis, the gap may reveal whether the problem is associated with excess additional unmeasured anions or with bicarbonate loss and chloride retention. In that sense, the calculator is less about arithmetic and more about spotting clinical patterns.
Typical Anion Gap Range and Interpretation
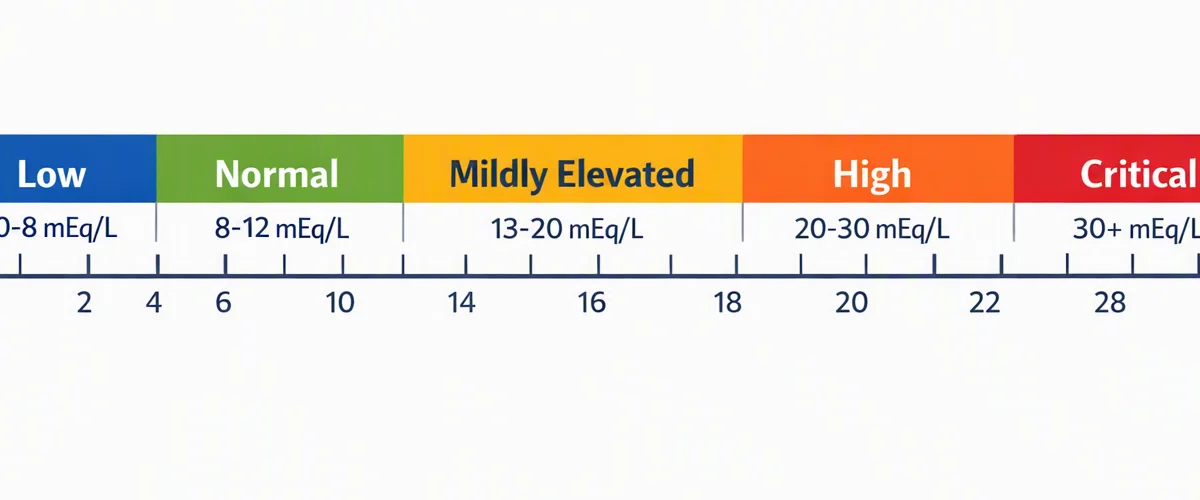
The normal range for anion gap varies by analyzer and approach, so the most important reference is against the local lab reference range. A value that appears high in one lab may be normal in another. This is why anion gap results should always be viewed in relation to the patient rather than in isolation.
A elevated anion gap usually suggests the presence of extra acids or other unmeasured substances that widen the gap. A reduced anion gap is less common and often reflects hypoalbuminemia, lab variation, or unusual ionic states rather than a primary acid-base disorder.
Analysis depends on the entire biochemical picture. For example, a borderline result in a stable patient may not be meaningful, while the same value in someone with vomiting, altered mental status, or shock may be a critical clue. The calculator is therefore best viewed as part of broader clinical evaluation, not a stand-alone answer.
Remember that the anion gap is influenced by the concentration of negatively charged proteins, especially serum albumin. Since albumin contributes substantial negative charge under normal conditions, a low albumin level can make the gap look falsely normal or low. That is one reason the raw number should always be read alongside the broader acid-base picture.
How the Anion Gap Helps Identify Acid-Base Disorders
The anion gap proves most helpful when assessing acid-base disorders, particularly when the question is whether metabolic acidosis is present and what type it may be. Practically speaking, it helps tell apart acid gain disorders and bicarbonate loss disorders.
In high anion gap metabolic acidosis, the body collects acids that are not directly measured on the chemistry panel. These acids increase the gap because bicarbonate falls as it buffers excess hydrogen ions, while chloride may not rise enough to fully compensate.
In normal anion gap metabolic acidosis, bicarbonate is lost and chloride rises in a compensatory pattern. The net gap may stay within the expected range even though the patient is clearly acidotic. This is why the anion gap calculator is so useful: it separates different metabolic patterns that can look similar on first inspection.
The gap can also be informative in mixed pictures involving respiratory alkalosis. For example, a patient may hyperventilate and lower carbon dioxide while also developing metabolic acidosis. In that setting, relying on one number can create a false sense of clarity. Careful analysis of pH, bicarbonate, and the anion gap helps detect a mixed disorder.
Overall, the calculator supports a structured approach to acid base balance. It helps clinicians move from a single abnormal lab result to a more complete interpretation of the underlying physiology.
Increased high anion gap acidosis causes
A high gap points toward added acids or retained acid equivalents. The classic causes include lactic acidosis, ketoacidosis, renal failure, and ingestion of toxic alcohols. Each condition raises unmeasured acid in the blood and moves the biochemical profile away from normal.
Lactic acidosis occurs when lactate production exceeds clearance, often in settings of tissue hypoperfusion, sepsis, severe exertion, or impaired metabolism. Because lactate is an unmeasured anion in routine chemistry, it can elevate the gap significantly.
Ketoacidosis is another important cause. It may be seen in diabetes, prolonged fasting, heavy alcohol use, or other states of carbohydrate deprivation. Ketone bodies such as beta-hydroxybutyrate and acetoacetate drive the rise in the gap and often accompany symptoms of dehydration, nausea, and altered mental status.
Renal failure can elevate the anion gap because the kidneys are unable to excrete acid effectively. As acids accumulate, bicarbonate falls and unmeasured acids rise. The result is a metabolic pattern that often points to advanced disease or sudden deterioration.
Toxic alcohols including methanol and ethylene glycol can also produce a high gap. These substances are metabolized into acidic compounds that create significant metabolic derangement. In the right setting, this pattern is a medical emergency and should prompt immediate evaluation.
Even though the anion gap does not identify the exact toxin or acid, it is a powerful clue that guides further testing and treatment. This is why it is frequently one of the first values reviewed in suspected poisoning or unexplained acidemia.
Normal Anion Gap Metabolic Acidosis Causes
A normal anion gap does not rule out acidosis. In normal anion gap metabolic acidosis, the key issue is often bicarbonate loss rather than accumulation of a new acid. The gap stays stable because chloride rises as bicarbonate falls, preserving the body's charge balance.
Frequent causes include diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. This pattern is often called hyperchloremic acidosis because chloride increases as bicarbonate decreases.
Diarrhea can cause substantial gastrointestinal bicarbonate loss, especially when long-lasting or intense. The kidneys may attempt to compensate, but the chemistry panel often shows low bicarbonate and high chloride with a near-normal anion gap.
Renal tubular acidosis refers to impaired renal handling of acid or bicarbonate. Depending on the subtype, the kidneys may fail to acidify urine properly or may waste bicarbonate. Either way, the result can be persistent metabolic acidosis with a normal gap.
Other conditions can resemble this pattern, including certain fluids, chronic kidney conditions, and mixed metabolic states. This is where careful interpretation matters: a normal gap should not stop the evaluation if the patient has a clearly low bicarbonate or a clinical picture consistent with acidosis.
The practical takeaway is simple: if the chemistry panel shows metabolic acidosis but the gap is not elevated, think about bicarbonate loss, chloride retention, and causes of hyperchloremic acidosis before assuming the problem is mild or resolved.
Accounting for the Anion Gap for Albumin
Since albumin serves as a major negatively charged protein in plasma, low albumin can mask a true rise in the anion gap. This is why albumin correction is an essential part of modern interpretation. If not corrected, a patient with significant acid accumulation may appear to have a normal result.
The corrected anion gap adjusts the measured value to account for hypoalbuminemia. The exact correction factor may vary slightly by formula, but the principle is the same: when albumin is low, restore a portion of the missing negative charge to determine the true gap more accurately.
This matters clinically because albumin contributes to protein binding and overall charge balance. If albumin falls, the measured gap may decrease even when unmeasured acids are present. In that situation, a seemingly normal anion gap may mask a clinically important high-gap process.
Albumin correction improves interpretation in patients with liver disease, malnutrition, critical illness, or inflammation, where hypoalbuminemia is common. It is especially useful when evaluating possible lactic acidosis, ketoacidosis, or toxin exposure in a patient whose chemistry panel does not appear striking at first glance.
In practice, the corrected value should be considered alongside pH, bicarbonate, and the rest of the electrolyte profile. The goal is not just to calculate a number, but to avoid missing a serious acid-base disorder because of altered protein levels.
Frequent Errors and Limitations
Although the anion gap calculator is useful, it has limitations. One of the most common issues is lab error. A hemolyzed sample, transcription problem, or analyzer variation can distort the result. When the number does not align with the clinical picture, repeating the test is often the best first step.
Another limitation is the presence of unmeasured cations. Substances such as lithium, severe magnesium elevation, or other cation excesses can lower the gap and obscure interpretation. Some medications may also alter acid-base status directly or indirectly, making the chemistry pattern less clear.
Interpretation errors commonly arise when providers focus on the anion gap alone and overlook the complete acid–base picture. The gap should be interpreted with pH, bicarbonate, carbon dioxide, and the patient’s overall status. Otherwise, a combined disorder or compensatory change may be overlooked.
One more pitfall is overlooking that a “normal” reading depends on the specific reference range. A value may be abnormal relative to one measurement and acceptable in a different one. That means any reading should be interpreted using the lab’s own reference interval rather than an assumed universal limit.
In the end, the anion gap does not identify the cause by itself. It is an indicator, not a medical diagnosis. Appropriate use requires relating the number to the broader picture of electrolyte balance, clinical findings, and likely exposures. This combination is what makes the calculator clinically useful.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is utilized to evaluate acid-base disorders, notably metabolic acidosis. It helps clinicians recognize whether the problem is more suggestive of a high-gap process such as lactic acidosis or ketoacidosis, or a normal anion gap process such as diarrhea or renal tubular acidosis. In that manner, it aids clinical use as a quick initial assessment and review tool.
How do you calculate the anion gap from lab values?
Use the the anion gap formula: sodium minus the total of chloride and bicarbonate. Put simply, anion gap = sodium − (chloride + bicarbonate). This calculation comes straight from a serum chemistry panel and is one of the most common methods of gap calculation in routine practice.
How does a elevated anion gap mean in acid base disorders?
A high anion gap usually means there are more unmeasured anions or hidden acids in the blood. In the setting of metabolic acidosis, that often points to lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. It is an valuable clue in acid-base analysis, but it still requires clinical context.
Why is the anion gap corrected the anion gap for albumin?
You account for albumin because reduced albumin can spuriously decrease the measured gap. With albumin correction, the corrected anion gap better reflects the true acid-base status, especially in hypoalbuminemia. This prevents missing a clinically important disorder when the raw value seems normal.
What leads to a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is commonly caused by diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. It is often described as hyperchloremic acidosis because chloride rises as bicarbonate decreases. If the bicarbonate is low but the gap is not elevated, these causes should be part of the diagnostic workup.