What Is the Anion Gap?
The anion gap is a computed value from routine electrolytes that assists clinicians in understanding a patient’s acid-base balance. It is usually based on sodium, chloride, and bicarbonate, and sometimes includes potassium depending on the formula used. In simple terms, the anion gap helps reveal unmeasured charged particles in the blood that can point to a metabolic acidosis or another acid-base disorder.
In a newborn or neonate, this number is interpreted differently than in older children or adults because neonatal physiology is still adjusting after birth. A newborn’s serum chemistry changes quickly during the first days of life, so the anion gap calculation must be viewed as part of the full picture, not as a isolated diagnostic marker.
The idea behind the anion gap is tied to the body’s buffer system. When acids rise or bicarbonate is depleted, the numbers shift, and the gap may increase. When chloride goes up or albumin falls, the gap may shrink. That is why understanding the relationship between serum sodium and serum chloride matters so much in neonatal assessment.
Expected Anion Gap Range in Infants
The usual reference range for the anion gap in newborns can change by laboratory, age after birth, and the formula used. In numerous settings, the expected value https://anion-gap-tracker244.cavandoragh.org/what-does-low-bicarbonate-along-with-a-high-anion-gap-mean is modestly different from adult values, especially in the initial days of life. A neonatal reference interval should always be evaluated using the lab’s own standards when available.
For newborn lab values, a normal anion gap is often considered to be in a general low-to-mid range, but the exact cutoff depends on whether potassium is included and how the lab measures electrolytes. Because serum bicarbonate can also shift during early adaptation, a single number is of less importance than the trend and the clinical picture.
A newborn may have a borderline or mildly altered gap without having a dangerous condition. However, if the anion gap is clearly elevated, clinicians often suspect metabolic acidosis and search for an underlying cause. Likewise, a low gap may suggest low albumin, excess chloride, or a testing issue.
It is important to remember that the normal range is not universal. A premature infant, a sick neonate, or a baby with abnormal hydration status may have values that deviate from a healthy term infant. For that reason, clinical interpretation should always include age, feeding status, respiratory status, and the rest of the serum chemistry panel.
What an Anion Gap Calculator Functions
An Anion Gap Calculator uses measured electrolyte values to approximate the unmeasured anions in the blood. A standard formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some calculators also include serum potassium:
Anion gap = (serum sodium + potassium) - (serum chloride + serum bicarbonate)
The result is a useful screening tool, especially when evaluating acid retention or a possible acid-base disturbance. In newborn care, the calculator is often used alongside a blood gas, a pH measurement, and the bicarbonate level to assess the infant’s condition more completely.
Albumin matters too. Because albumin is a major unmeasured anion, low albumin can make the gap look falsely normal or low. For this reason a calculator may be helpful, but it does not replace professional interpretation. In a baby with illness, the same numeric result can mean something very different depending on hydration, renal status, and the presence of systemic illness.
Helpful rule: the anion gap is a clue, not a diagnosis. In newborns, it works best when paired with the blood gas, pH, bicarbonate level, and overall clinical context.
Why Newborn Anion Gap Values Can Differ From Adults
Multiple characteristics of neonatal physiology help explain why newborn values can vary from adult values. After birth, the infant transitions from placental support to independent breathing, circulation, and kidney function. This quick shift affects electrolyte handling and acid-base balance.
Prematurity can cause these differences more apparent. A preterm infant may have immature kidneys, reduced acid excretion, and less consistent buffering capacity. As a result, the same serum chemistry pattern may have a distinct meaning than it would in an older child. The developing kidney plays a major role in chloride reabsorption, bicarbonate conservation, and overall electrolyte balance.
Kidney performance is especially important in the early neonatal days. A newborn kidney is still learning to manage sodium, chloride, fluid, and acid handling. This can influence the Anion Gap Calculator and other laboratory results. A temporary shift does not necessarily indicate disease, but ongoing abnormalities warrant attention.
Infants also have rapid changes in body fluid distribution, nutrition, and metabolic function. These changes can alter the buffer system and the shift in chloride. As a result, pediatric interpretation relies on developmental reference interval data rather than adult assumptions. A elevated anion gap or reduced anion gap should be interpreted as part of a broader metabolic evaluation.
Common Causes of a High Anion Gap in Newborns
A high anion gap in a newborn often points to the presence of additional acids in the blood. This is a major finding in metabolic acidosis and can signal a serious problem that calls for prompt evaluation. The most common causes include:
- Lactic acidosis, often related to poor oxygen delivery, poor circulation, or severe illness Sepsis, which can cause tissue hypoperfusion and systemic illness Ketoacidosis, less common in newborns but possible in certain metabolic or feeding-related states Inborn errors of metabolism, which may interfere with normal acid handling and energy production
Lactic acidosis is a serious concern because it can show inadequate oxygen delivery or impaired perfusion. In a sick newborn, this may develop with infection, respiratory compromise, or circulatory instability. The anion gap rises because lactate is an unmeasured anion that builds up in the bloodstream.
Sepsis is another critical cause. A newborn with sepsis may show poor feeding, temperature instability, lethargy, abnormal breathing, or worsening lab results. The acid-base disorder may be subtle at first, so the anion gap can provide an early clue that something is wrong.
Inborn errors of metabolism are especially important in neonatal evaluation because they may present with a high anion gap before the diagnosis is obvious. These disorders can cause acid retention, abnormal ammonia levels, or worsening metabolic disturbance after feeding starts. When the gap is elevated without a clear explanation, clinicians often expand testing promptly.
Ketoacidosis is less common in a newborn than in older patients, but it can occur in specific settings where energy metabolism is disrupted. Regardless of the cause, a high gap should be treated as a signal to investigate the full clinical picture rather than as an isolated number.
Frequent Reasons of a Usual or Reduced Anion Gap
A regular anion gap does not always mean all is well, and a low anion gap can be helpful. In neonates, the main reasons include hypoalbuminemia, hyperchloremia, or a measurement issue such as lab error.
Hypoalbuminemia is notable because albumin affects the measured equilibrium of charged particles. If protein levels are decreased, the gap may be reduced even when another process is present. This can make interpretation tricky, especially if the baby is ill or has fluid shifts that dilute blood proteins.
Hyperchloremia can also decrease the anion gap. When chloride rises compared with sodium and bicarbonate, the calculated gap decreases. This can happen after certain IV fluids, with renal handling changes, or during specific acid-base disturbances. In some cases, the pattern may suggest a non-gap metabolic acidosis rather than a high-gap disorder.
Lab error should always be considered if the result does not fit the infant’s condition. Repeating the test may be warranted if the values are unexpected, especially when the baby looks clinically well or the numbers conflict with the blood gas. A mismatch between the anion gap and the overall serum chemistry can point to sampling problems or analytical variation.
When the anion gap is typical, it does not fully exclude disease. A newborn can still have serious illness, especially if the bicarbonate level is low or the blood gas shows abnormal pH. That is why the gap should be used as one part of a larger metabolic evaluation.
How to Read Findings Carefully
Safe analysis starts off with the blood gas, pH, and bicarbonate as a group. No single result can determine a diagnosis. The anion gap helps sort an acid-base disorder, but it must be paired with the baby’s symptoms, feeding routine, breathing work, and other lab results.
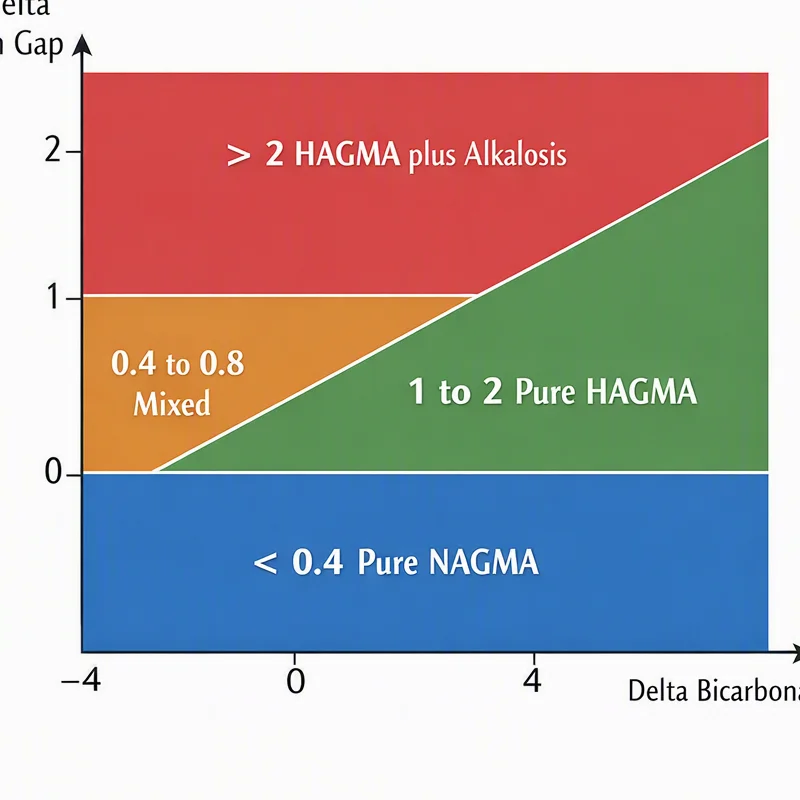
If the bicarbonate level is low and the pH is acidemic, the clinician looks closely at the gap to see whether the acidosis is high-gap or non-gap in nature. A high gap may suggest lactate, ketones, toxins, or metabolic disease. A normal gap may suggest bicarbonate loss or chloride gain. Both patterns may matter in a newborn.
Clinical context matters more than any single cutoff. A baby with mild lab changes but normal activity and feeding may be monitored differently than a baby with poor perfusion, respiratory distress, or signs of infection. The same numeric result can have different interpretation depending on age in hours, hydration, and whether the infant is premature.
If the result is unexpected, clinicians may repeat the serum chemistry, review the collection method, and compare it with the blood gas. This helps confirm whether the abnormality is real and whether it reflects a true metabolic disturbance or a measurement issue. For newborn care, accurate interpretation is part of careful neonatal assessment, not just formula use.
When to Get Prompt Medical Review
Prompt medical review is needed when a newborn has concerning symptoms plus abnormal lab results. Important signs include respiratory distress, poor feeding, lethargy, and dehydration. These symptoms may point to whole-body illness, infection, impaired circulation, or a significant metabolic problem.
Respiratory distress may present as rapid breathing, grunting, flaring nostrils, or chest retractions. This can affect acid-base balance and may be linked to a rising anion gap or abnormal pH.
Poor feeding and lethargy are especially important in a neonate because they can be initial signs of sepsis or inborn errors of metabolism. If a newborn is hard to arouse, nurses poorly, or becomes less responsive, immediate evaluation is warranted.
Dehydration can also alter electrolyte patterns and worsen acid retention. Signs may include decreased urine output, dry mucous membranes, or excessive weight loss. In some cases, dehydration contributes to both clinical instability and altered serum chemistry.
If symptoms are present, do not rely on the anion gap alone. A prompt blood gas, pH assessment, repeat electrolytes, and broader metabolic evaluation may be needed. This is especially true when prematurity, renal function concerns, or suspected infection are part of the picture.
Frequently Asked Questions
What is the expected anion gap in newborns?
The typical anion gap in newborns depends on the lab’s reference range, the calculation formula, and the baby’s age after birth. Many newborn lab values fall within a broader reference interval than adult values. Because serum bicarbonate and other electrolytes shift quickly in early life, the best interpretation uses the lab’s own reference range plus the newborn’s clinical status.
Is the normal anion gap in newborns different from adults?
Indeed. The typical anion gap in newborns can differ from adults because of neonatal physiology, prematurity, and immature renal function. Newborns are still adjusting their acid-base balance, so pediatric interpretation should use age-appropriate standards rather than adult assumptions.
How do you apply an Anion Gap Calculator for a newborn?
An Anion Gap Calculator uses serum sodium, serum chloride, and serum bicarbonate, and sometimes potassium, to determine the gap. For newborns, it should be used together with albumin, a blood gas, and the bicarbonate level. The result supports shape clinical interpretation, but it does not replace a full neonatal assessment.
What does a high anion gap mean in a newborn?
A high anion gap in a newborn suggests unmeasured acids in the blood and may point to metabolic acidosis. Common causes include lactic acidosis, sepsis, ketoacidosis, and inborn errors of metabolism. Because these can be serious, a high gap should always be assessed in clinical context.
Can a normal anion gap still be serious in a newborn?
Yes. A normal anion gap does not eliminate illness. A newborn can still have respiratory distress, sepsis, dehydration, or another acid-base disorder with a normal gap. That is why blood gas results, pH, bicarbonate, and the overall clinical picture are crucial for safe interpretation.