If you want to calculate anion gap values accurately, the key is grasping how the anion gap is built from routine electrolytes and why low albumin can conceal a clinically important abnormality. An Anion Gap Calculator can streamline the math, but the real advantage comes from knowing how to interpret the result in acid-base analysis.
Defining the Anion Gap?
The anion gap is a calculated number that helps measure the difference between measured positive and negative charges in the blood. It is usually calculated from common lab values on a blood test, especially sodium, chloride, and bicarbonate. In many cases, potassium may also be added depending on the formula being used.

Clinically, the anion gap is a helpful diagnostic aid in evaluating an acid-base disorder. It helps identify whether an unexplained metabolic acidosis may be present and whether the cause is likely to be due to unmeasured acids, changes in proteins, or shifts in serum electrolytes. The https://anion-gap-results937.wordcanopy.com/posts/anion-gap-calculator-for-blood-chemistry-interpretation calculation is part of a larger metabolic panel or basic metabolic panel, which provides a overview of key lab values.
The concept is straightforward: blood contains positively charged ions and negatively charged ions. The measured ions do not account for everything present, so the “gap” represents unmeasured components. A normal result falls within a reference range that varies slightly by laboratory and by whether potassium is included in the formula.
How the Anion Gap Calculator Works
An anion gap calculator is intended to simplify the gap calculation using the lab values entered from a basic metabolic panel or similar electrolyte test. In most cases, the calculator uses sodium, chloride, and serum bicarbonate. Certain versions also accept potassium, which slightly alters the formula.
At its core, the calculator applies an anion gap formula such as:
Anion gap = Sodium − (Chloride + Bicarbonate)
If potassium is included, the formula becomes:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
This calculated measurement can help reduce math errors and make interpretation faster when reviewing serum electrolytes. The calculator may also help highlight values that are outside the normal range, which is especially helpful when assessing possible electrolyte imbalance or an acid-base disorder.
However, the calculator is only as useful as the data provided. A missing or inaccurate lab value can lead to incorrect interpretation. That is why the clinical significance of the number depends on the full lab context, especially the bicarbonate level, the patient’s albumin status, and any evidence of acid-base disturbance.
Corrected Anion Gap: Overview and Formula
The effective anion gap is the anion gap adjusted for the effect of albumin, which is the main anion-bearing protein in blood. Because albumin has a strong effect on the normal anion gap, a low albumin level can make the gap appear artificially normal. That is where albumin correction becomes important.
The purpose of this correction is to better reflect true acid-base equilibrium. In a patient with hypoalbuminemia, the measured gap may underestimate the presence of unmeasured acids. The adjusted value is sometimes called the adjusted anion gap.
A common correction formula is:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − serum albumin in g/dL)
This is an albumin correction factor used to estimate how much the low albumin is lowering the result. Different references may use slightly different factors, but the goal is the same: account for albumin so the interpretation is more accurate.
Why does this matter? Albumin is one of the major negative proteins in plasma. When it drops, the body may preserve electroneutrality by increasing chloride or bicarbonate-related shifts, and the anion gap can look deceptively normal. Using the effective value improves clinical interpretation in acid-base analysis.
Step-by-Step: How to Calculate Effective Anion Gap
To calculate the effective anion gap, use a simple stepwise approach using the available lab values. This is the practical method clinicians use when reviewing serum electrolytes and deciding whether the patient has a hidden high-gap disorder.
Step 1: Identify the lab values from the blood test.
- Sodium Chloride Bicarbonate Serum albumin
Step 2: Determine the measured anion gap using the standard formula.
Anion gap = Sodium − (Chloride + Bicarbonate)
Step 3: Compare the result with the laboratory reference range.
Step 4: If albumin is low, follow the calculation formula for albumin adjustment.
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − serum albumin)
Step 5: Assess the corrected anion gap in the context of the patient’s acid-base state.

This is a worked example. Imagine the labs show:
- Sodium: 140 Chloride: 104 Bicarbonate: 18 Serum albumin: 2.0 g/dL
Measured anion gap:
140 − (104 + 18) = 18
Albumin correction:
Corrected anion gap = 18 + 2.5 × (4.0 − 2.0)
Corrected anion gap = 18 + 5 = 23
In this example, the measured result is elevated, and the albumin-adjusted value is even higher. This suggests a more significant underlying problem than the raw number alone would show.
When you use an Anion Gap Calculator, make sure to check whether the tool includes albumin correction. Some tools provide only the standard result, while others display both the measured and corrected values. In a clinical setting, the adjusted result can be especially helpful when the serum albumin is low.
Why Albumin Alters the Anion Gap
Low albumin changes the anion gap because albumin holds a negative charge and functions as a major unmeasured anion in plasma. When albumin falls, the body’s charge balance shifts, often reducing the observed anion gap even if a true acid-base problem exists.
This is why albumin matters so much in acid-base balance. In people with low albumin, a normal anion gap may not actually rule out a high-gap process. Without adjustment, the lab pattern can look less abnormal than it truly is.
Several physiologic factors play a role in this effect:
- Albumin is a major source of unmeasured negative charge. Shifts in protein binding can alter the distribution of ions. The body may compensate by shifting chloride or bicarbonate.
Because of this, clinicians often rely on albumin correction when the clinical picture suggests an acid-base disorder but the basic calculation seems borderline. In that setting, the corrected number gives a better estimate of the true gap.
How to Read the Result
Understanding the anion gap is not just about determining whether the number is high or normal. It is about relating the measurement to the overall acid base picture. A high anion gap often indicates the presence of unmeasured acids and can be seen in metabolic acidosis.
Frequent high-gap processes include lactic acidosis and ketoacidosis. In both settings, acid accumulates and bicarbonate is consumed, which elevates the gap. If the corrected value is elevated, the finding becomes even more important because low albumin may have masked the severity of the problem.
On the other hand, a normal result does not always mean the problem is resolved. A normal anion gap can still occur in metabolic acidosis, particularly when bicarbonate falls and chloride rises in a way that maintains the calculated difference. This is why the result should be interpreted alongside pH, bicarbonate, and the rest of the clinical assessment.
Practical interpretation tips:
- A high corrected gap supports a high-gap metabolic acidosis. A normal measured gap with low albumin may still hide an elevated corrected gap. Trend changes can be more informative than a single value. Always compare the result with the patient’s symptoms and other lab values.
The main goal of gap calculation is to guide thoughtful clinical interpretation, not to replace it. The number is a tool for recognizing patterns in serum electrolytes and for identifying whether extra workup is needed.
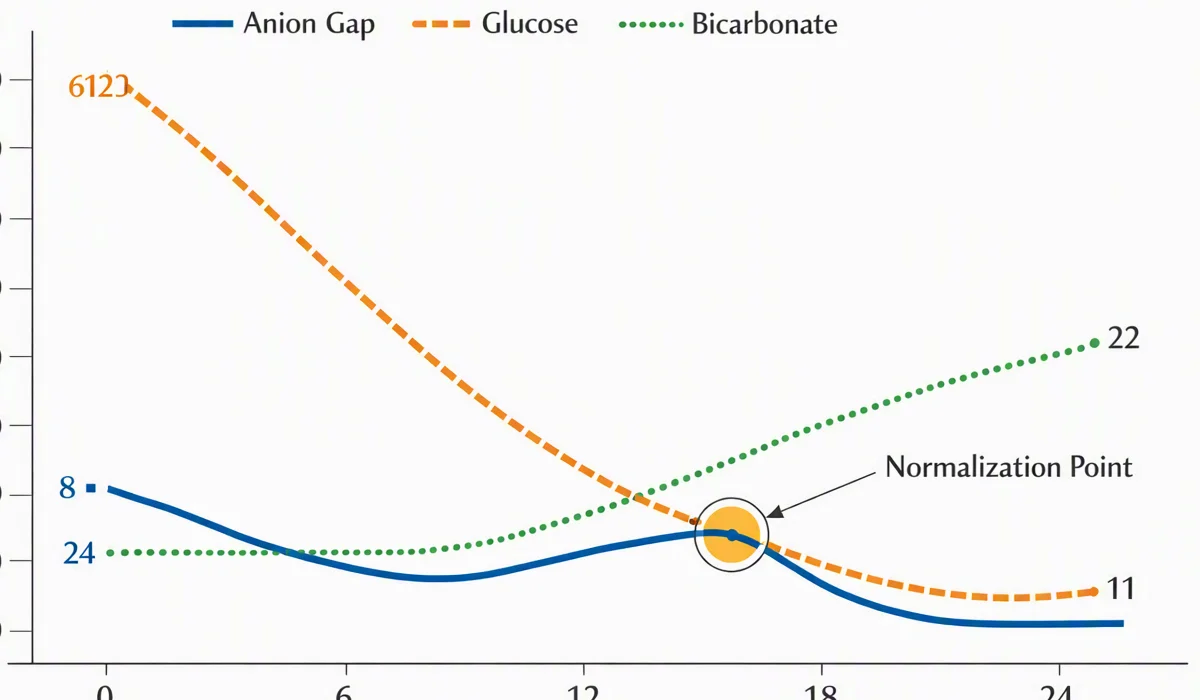
Common Causes of a High or Decreased Anion Gap
Many conditions can alter the gap higher or downward. A elevated anion gap often indicates acid buildup, while a low result may suggest a shift in proteins, lab methods, or higher-than-normal chloride. Understanding the cause helps relate the number to the patient’s overall status.
Frequent causes of a high anion gap include:
- Lactic acidosis, due to tissue hypoperfusion, sepsis, or other causes of impaired oxygen delivery Ketoacidosis, including diabetic ketoacidosis, starvation ketoacidosis, or alcohol-related ketosis Renal failure, where acid excretion is reduced and unmeasured acids accumulate Toxic alcohols, such as methanol or ethylene glycol, which can generate acid metabolites
Common causes of a low or surprisingly normal gap include:
- Hyperchloremia, which can offset bicarbonate loss and keep the calculation from rising Low albumin levels, which lowers the measured value Laboratory variation or measurement issues that affect sodium, chloride, or bicarbonate Higher unmeasured cations in certain uncommon settings
Certain conditions, such as renal failure, may also produce mixed findings depending on the stage and the patient’s fluid status. Likewise, toxic alcohols often need rapid identification because the gap may rise before other symptoms become obvious.
An additional important cause of an unusual low or altered result is multiple myeloma. This condition can affect protein composition in the blood and change how the calculation behaves, which is one reason albumin and total protein context matter.
When the pattern seems unclear, revisit the basic metabolic panel, the albumin level, and the correction formula. A careful review of lab values often reveals why a seemingly simple blood test produces a complex result.
Frequently Asked Questions
How do you calculate the anion gap?
The most common anion gap calculation is sodium minus chloride and bicarbonate added together: sodium − (chloride + bicarbonate). Some versions also include potassium, but many routine calculations use the basic form from a basic electrolyte panel. The exact formula depends on the laboratory and the clinical assessment being used.
How do you adjust the anion gap for albumin?
First calculate the initial anion gap from the electrolyte panel. After that, use the albumin adjustment factor: corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin). This correction helps correct for albumin so low albumin does not mask a true gap abnormality.
Why correct the anion gap for albumin?
Albumin is a major negatively charged protein in blood, so shifts in albumin alter the gap calculation. In hypoalbuminemia, the measured gap may look falsely low or normal. Correcting for albumin improves the accuracy of acid-base evaluation and the overall assessment of acid-base equilibrium.
What does a high anion gap mean?
A high anion gap usually suggests the presence of unmeasured acids and is commonly associated with metabolic acidosis. Important causes include lactate buildup, ketone accumulation, kidney failure, and toxic alcohols. The result should always be interpreted alongside symptoms and other lab values.
Can the anion gap be normal even when metabolic acidosis is present?
Yes. A unchanged anion gap can occur even with metabolic acidosis, especially when bicarbonate falls and chloride rises in a way that preserves the calculation. This is one reason the result should be reviewed in the context of the entire metabolic panel, serum albumin, and the overall clinical picture.
In real-world use, an Anion Gap Calculator is especially useful when it supports a stepwise evaluation of the blood test: note the electrolytes, determine the raw gap, calculate anion gap using the standard formula, then corrected anion gap values when albumin is low. That process offers a clearer picture of whether the patient has a genuine acid-base disorder or a result that requires further investigation.