What Is the Anion Gap?
The anion gap is a basic but valuable value derived from routine electrolytes on a serum chemistry panel. It helps clinicians identify hidden acids or other unmeasured anions that may be affecting a patient’s chemistry. In practical terms, the anion gap value supports clinical interpretation of blood chemistry by showing whether there may be an underlying electrolyte imbalance or metabolic acid-base disorder.
The classic anion gap formula compares positively charged ions with negatively charged ions, most commonly using serum sodium, serum chloride, and serum bicarbonate. In many lab systems, potassium may also be included, although the most common version excludes it. The result is not a direct measurement of acid, but a diagnostic aid that can indicate conditions that require more detailed acid-base evaluation.
Because the anion gap is calculated from standard laboratory results, it is widely used in bedside and outpatient patient assessment. A careful review of the number can suggest whether there is a high anion gap pattern, a normal anion gap state, or an unexpectedly low anion gap that deserves confirmation.
Why the Corrected Anion Gap Counts
This usual anion gap is valuable, but it can be deceptive when albumin is low. Because serum albumin holds a significant amount of negativity in the blood, hypoalbuminemia can lower the measured gap even when important acids are present. This is why the corrected anion gap is useful: it adjusts the number so the clinician can more accurately assess acid-base balance.
Without albumin adjustment, a patient with significant metabolic acidosis may seem to have a comforting result. That is especially important in hospitalized or critically ill patients, where albumin may drop because of inflammation, poor nutrition, fluid shifts, or illness severity. In these cases, the corrected value improves diagnostic interpretation and supports more accurate decisions.
The corrected result is not meant to override clinical judgment. Instead, it adds context to the raw calculation and improves clinical significance. For example, a “normal” anion gap in a patient with low albumin may still mask a true acid load. This is why correction is often a truer reflection of real physiology than the unadjusted number alone.
How the Anion Gap Calculator Works
The Anion Gap Calculator simplifies the anion gap calculation so clinicians and students can quickly calculate the gap from routine blood chemistry. Most calculators apply a simple calculation formula based on serum sodium, serum chloride, and serum bicarbonate. In its standard form, the calculation is:
anion gap = sodium - (chloride + bicarbonate)Some versions also include potassium, which modestly changes the result. A potassium-inclusive formula may be written as:
anion gap = sodium + potassium - (chloride + bicarbonate)Both versions are applied in practice, but the sodium-based formula is the most common. The calculator does not diagnose disease by itself; it is a diagnostic aid that helps assess the broader pattern of blood chemistry. When paired with the patient’s symptoms, pH, lactate, ketones, kidney function, and medication history, it becomes part of a complete clinical interpretation.
Because the anion gap reflects the difference between measured cations and measured anions, it indirectly indicates the presence of unmeasured anions. That is why it is so valuable in detecting metabolic problems that might otherwise be overlooked on a standard serum chemistry panel.
Adjusting the Anion Gap for Albumin
The adjusted anion gap takes into account the influence of serum albumin. Because albumin is a key negatively charged protein, decreased levels can make the gap seem falsely low or within range. The correction for albumin updates the number upward when albumin is below the normal reference interval.
A typical correction approach uses a fixed amount for each gram https://pastelink.net/e934j777 per deciliter that albumin is below normal. Some institutions may use slightly different formulas, so the exact adjustment may vary. In general, the lower the albumin, the greater the need for recalculation. This is the practical heart of gap correction.
Why does this matter? Because hypoalbuminemia can mask a true metabolic acidosis. A patient may have a standard anion gap that looks unremarkable, yet the corrected value reveals a clinically significant elevation. That difference can change the workup, the urgency of treatment, and the interpretation of the overall acid-base state.
Understanding the corrected result is very important when comparing values against a lab’s reference range. A “normal” uncorrected number may no longer be normal after albumin correction. For this reason, the corrected calculation is often a better reflection of the patient’s true clinical meaning than the raw value alone.
Typical Causes of an Elevated Anion Gap
An raised gap commonly points to presence of acids or unmeasured anions. The main causes are lactic acidosis, ketone acidosis, renal failure, and specific toxic ingestions. These states can each disturb the acid-base balance and create a distinct elevated anion gap pattern.
Lactic acidosis can occur when tissues are underperfused or struggling metabolically, leading to higher lactate production. Ketoacidosis occurs when ketone bodies accumulate, often in diabetes, alcohol-related illness, or prolonged fasting. Renal insufficiency can increase the gap because the kidneys are unable to remove acids effectively.
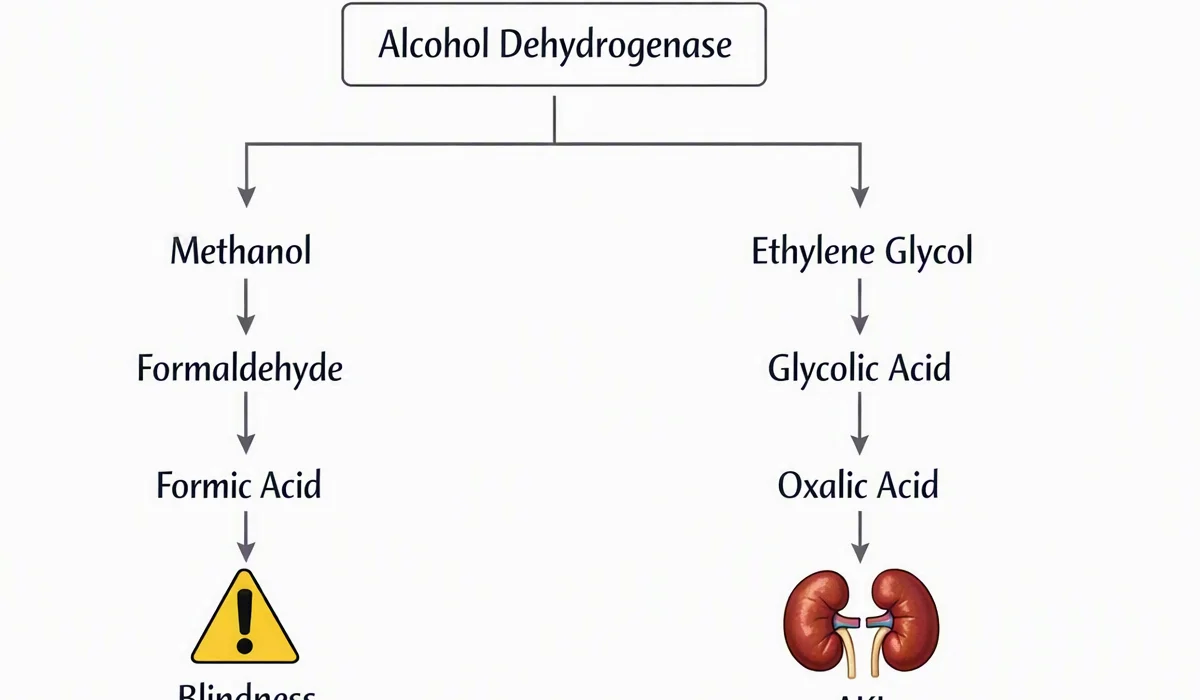
Poisonous alcohols are another significant cause of increased values. Ingestions involving methanol, ethylene glycol, and related compounds can produce serious acid-base derangements that may be life-threatening. Salicylate drugs can also alter the pattern, sometimes creating a mixed disorder that requires careful review of the full clinical picture.
Because these disorders can overlap, the anion gap should be viewed as a single part of the puzzle. It supports clinical evaluation, but it does not replace history, exam, medication review, and targeted testing. The calculator is most useful when it guides the following step in the diagnostic process.
How to Understand Low and Normal Anion Gap Results
A reduced anion gap is rarer than an elevated one, but it can still matter. Before assuming disease, the first question is whether the result is real. Lab error is one of the most frequent explanations, so repeating the sample is often the first step if the result is unexpected.
A within-range anion gap does not always mean there is absence of acid-base disorder. If the patient has hypoalbuminemia, the true gap may be missed until an albumin correction is applied. That is why the modified number can be more revealing than the initial number when assessing metabolic acidosis.
Another important cause of a decreased or unexpectedly normal result is paraproteinemia. Abnormal proteins can distort the blood chemistry pattern and change the apparent balance of measured ions. In such cases, the anion gap is not a diagnosis by itself, but a signal that may prompt additional workup.
When interpreting low or normal results, look at the entire clinical interpretation: albumin level, other electrolytes, pH, bicarbonate, kidney function, and the patient’s symptoms. This broader approach enhances diagnostic interpretation and helps avoid false reassurance.
Step-by-Step Example Calculation
Here is a basic sample calculation using common laboratory values. Let’s say the patient has the following:
- serum sodium: 140 chloride level: 102 serum bicarbonate: 18 potassium: 4.0
Using the common sodium-based formula, the calculation is:
anion gap = 140 - (102 + 18)This results in an anion gap of 20. Provided that the lab’s reference range is lower than that, this may indicate a elevated anion gap. Should the patient also has low albumin level, the next step is albumin adjustment to determine the albumin-corrected anion gap.
At this point assume the albumin is reduced. Once applying the appropriate anion gap adjustment, the corrected value may be even higher, revealing a more significant metabolic problem than the unadjusted number suggested. This is why the Anion Gap Calculator is a highly practical diagnostic aid: it makes easier the math while keeping the clinical meaning.
This sample calculation also shows how the result connects to the rest of the evaluation. A high gap with low bicarbonate can support concern for acid-base imbalance, while the underlying cause may be elevated lactate, ketone-related acidosis, renal failure, alcohol toxins, or salicylate toxicity. The calculator does not identify the cause, but it assists in narrowing the differential.
Frequently Asked Questions About Adjusted Anion Gap Results
What is a corrected anion gap and why is it used?
The anion gap adjusted for albumin is the regular anion gap corrected for low serum albumin. It is used because hypoalbuminemia can make the uncorrected value look misleadingly normal. The correction improves clinical interpretation and more accurately shows the patient’s true acid-base balance.
How is calculated the anion gap with albumin correction?
Start with the usual anion gap formula using serum sodium, serum chloride, and serum bicarbonate. Then add an albumin correction based on the measured serum albumin. The exact method may change by institution, so the calculator should follow the same reference range and formula used by the lab or clinical setting.
What may suggest a high anion gap?
A high anion gap commonly suggests extra acids in the blood, such as in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols or salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with the rest of the laboratory results and the patient’s symptoms.
Can a normal anion gap still mean a serious problem?
Yes. A normal anion gap does not always rule out clinically important illness. Hypoalbuminemia can hide a true gap, and a lab error can also distort the result. In addition, a patient may have another type of metabolic problem that requires broader acid-base evaluation and clinical review.
When should an anion gap result be reviewed by a clinician?
Any unexpected result should be reviewed when it does not fit the patient’s condition, especially if there is metabolic acidosis, altered mental status, kidney dysfunction, suspected poisoning, or significant electrolyte imbalance. The result is best used as a diagnostic aid within overall patient assessment, not as a standalone answer.