What Is an Anion Gap?
The anion gap is a calculated value used in laboratory interpretation to help assess acid-base balance and identify certain acid-base disorders. It compares the main measured electrolytes in blood, especially sodium, chloride, and bicarbonate, to estimate the balance between unmeasured positively and negatively charged particles in the bloodstream.
In simple terms, the anion gap reflects charge balance in a blood sample. A normal value suggests the measured ions are in a typical relationship, while an abnormal result can be a diagnostic clue for conditions such as metabolic acidosis or a protein-related change in serum chemistry. Because the result comes from a formula rather than a direct measurement, understanding the underlying pathophysiology matters.
The anion gap is often used as a screening test during workups of unexplained illness. It does not diagnose a disease by itself, but it helps clinicians think through the cause of an electrolyte imbalance and decide what to test next.
How an Anion Gap Calculator Operates
An anion gap calculator relies on values from standard blood test results to compute the anion calculation. Most commonly, it uses serum sodium, serum bicarbonate, and serum potassium, though potassium is often excluded depending on the formula employed by the lab or calculator. The goal is to estimate the difference between recorded cations and anions.
A typical version of the formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some calculators also incorporate potassium, which slightly changes the result. Whatever the formula, the key idea is the same: the calculation helps identify shifts in electrolytes that may indicate an underlying problem with acid-base status.
Using an anion gap calculator is useful because it cuts down on manual errors and gives a rapid estimate of whether the result stays inside the expected reference range. Still, the number should always be interpreted with the rest of the blood chemistry panel, not in isolation.
Does Hyperproteinemia Alter the Anion Gap?
Yes, hyperproteinemia can affect the anion gap, and in many cases it may contribute to a low anion gap. The effect depends on the kind and amount of protein present, especially the balance of albumin, paraproteins, and other plasma proteins. This is where https://anion-gap-tool502.bearsfanteamshop.com/anion-gap-calculator-with-blood-potassium-input the medical relevance becomes important: not all protein elevations affect the anion gap in the same way.
Albumin is one of the most important unmeasured anions in blood. When albumin is low, the anion gap may decrease. But hyperproteinemia can also involve excess abnormal proteins, especially paraproteins, which may behave differently from normal albumin. Some of these proteins can carry a positive charge and lower the apparent anion gap by changing the overall charge balance in serum.
This is why a protein-related abnormal result can be a helpful diagnostic clue. In some cases, hyperproteinemia points to a larger systemic disease, and the anion gap calculator becomes one piece of the diagnostic interpretation rather than the final answer.
How Changes in Proteins Can Affect Lab Results
Abnormal proteins can affect lab results because proteins contribute to the charge balance of blood. Some of these proteins act as cationic proteins, while others are closer to negatively charged proteins. When the concentration or kind of protein varies, the measured electrolyte balance can move even if sodium, chloride, and bicarbonate appear only mildly changed.
In practical terms, this means an increase in abnormal proteins can cause a measurement artifact or a true biochemical shift. A lab artifact does not mean the result is useless; it means the number may not show the full clinical picture without context. This is why laboratory interpretation should always consider protein concentration, acid-base status, and the patient’s overall condition.
Hyperproteinemia may also interact with routine assays in ways that influence how results are reported. While modern laboratory methods are highly reliable, no test is perfect. A pattern that seems inconsistent with the patient’s symptoms may reflect a lab artifact, a protein-related shift, or both. Understanding this helps avoid overcalling acid-base disorders or missing an important underlying diagnosis.
Frequent Causes of Hyperproteinemia
Several conditions can cause hyperproteinemia, and the cause often shapes the effect on the anion gap. One of the simplest causes is dehydration, which decreases plasma water and causes proteins to seem more concentrated. In that situation, the protein concentration rises relative to the fluid portion of blood, but the clinical effect on the anion gap may be modest unless other abnormalities are present.
More important causes include multiple myeloma and monoclonal gammopathy, both of which can increase abnormal immunoglobulins in the blood. These paraproteins may shift charge balance and create a low anion gap. This is a classic laboratory interpretation pitfall because the anion gap may be the first clue that triggers further workup.
Chronic inflammation can also raise total protein by increasing certain globulins. In these cases, hyperproteinemia may reflect a persistent systemic disease rather than a primary blood disorder. The pattern of protein changes, along with the rest of the serum chemistry, helps determine whether the finding is benign, transient, or clinically important.
Low Anion Gap vs Elevated Anion Gap: What to Check For
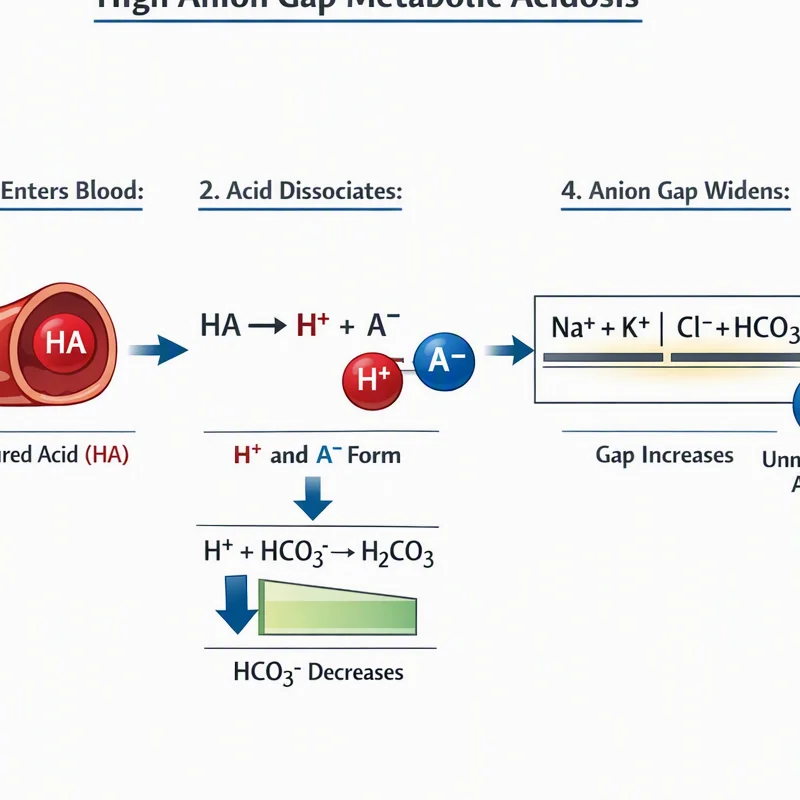
A decreased anion gap is the finding most often linked to hyperproteinemia, especially when paraproteins are present. Unusual proteins can lower the calculated gap by shifting the balance of unmeasured ions. In contrast, high anion gap metabolic acidosis usually points to excess acids in the blood, such as lactate or ketones, and is not typically caused by protein excess alone.
This distinction is important because a high gap and a low gap have different clinical meaning. A low gap may suggest protein abnormalities, medication effects, or a lab-related issue, while a high gap more often suggests metabolic acidosis. That said, both can occur in complex illness, so the result should always be viewed alongside symptoms and the rest of the panel.
Albumin correction is especially useful when a low albumin level might be hiding the true acid-base status. Since albumin is a major unmeasured anion, low albumin can lower the anion gap and make the value seem less concerning than it really is. Correcting for albumin helps estimate a corrected anion gap and makes the result more accurate for detecting acid-base disorders.

How to Interpret Values in Clinical Context
Interpreting the anion gap correctly requires looking at more than one number. The best clues often come from serum albumin, total protein, and the full blood chemistry panel. If total protein is high and the anion gap is low, hyperproteinemia becomes more relevant. If albumin is low, the gap should be adjusted before drawing conclusions about acid-base status.
Clinicians also consider the broader acid-base status. For example, a patient with metabolic acidosis and a normal gap may still have a serious illness, while a low anion gap with no symptoms may indicate a protein-related issue or an artifact. The same number can mean something different depending on the rest of the blood test findings.
This is where anion gap calculator is particularly valuable: it gives a useful starting point for diagnostic interpretation, but the meaning of the result depends on the clinical context. A single number cannot explain the whole story. Symptoms, medications, hydration, kidney function, and protein studies all influence the final interpretation.
When to Recheck or Add More Lab Tests
If the result appears unusual, repeat lab testing is frequently the initial step. Checking the sample again can help rule out specimen errors, processing issues, or a basic calculation error. A repeat result also helps determine whether the abnormality is lasting or short-lived.
If protein abnormalities are suspected, protein electrophoresis is a common next test. It can help detect monoclonal proteins and differentiate causes such as multiple myeloma or monoclonal gammopathy from more nonspecific protein elevation. In certain cases, a complete complete metabolic panel or other specific blood studies are needed to better define the clinical picture.
The choice to order additional tests should consistently rely on clinical correlation. If the patient feels well and the abnormality is mild, the finding may not require immediate action. If symptoms, renal issues, anemia, bone pain, or other signs point to a plasma cell disorder, additional testing becomes more important. The anion gap should guide evaluation, not substitute for it.
FAQ: Hyperproteinemia and Anion Gap
Can hyperproteinemia lower the anion gap?
Yes. Hyperproteinemia can reduce the anion gap, especially when the elevated proteins are paraproteins or other positively charged proteins. These proteins can alter charge balance and create a decreased anion gap on laboratory testing.
Does hyperproteinemia cause a high or low anion gap?
It most often causes a low anion gap rather than a high one. A high anion gap metabolic acidosis usually points to excess acid buildup, while protein excess is more likely to lower the calculated gap.
Should albumin be corrected when using an anion gap calculator?
Absolutely, albumin correction is important to do when serum albumin is low. Since albumin strongly affects the anion gap, correcting for it can reveal the corrected anion gap and improve diagnostic interpretation.
What laboratory conditions can make the anion gap look abnormal?
A number of lab issues can influence the result, such as measurement error, alterations in electrolytes, low serum albumin, and abnormal plasma proteins. Evaluating the full blood chemistry panel helps determine whether the abnormal result is genuine or deceptive.
When should additional testing be done after an abnormal anion gap result?
Additional testing is appropriate when the abnormality is ongoing, unexplained, or paired with symptoms or other abnormal blood test results. Protein electrophoresis, repeat lab testing, and a complete metabolic panel are typical follow-up studies when hyperproteinemia or a plasma cell disorder is suspected.