What the Anion Gap Is Measured
The anion gap is a computed value that allows clinicians to evaluate electrolytes and broader acid-base balance. It is not directly measured on a blood test; instead, it is calculated from common lab values, particularly sodium, chloride, and bicarbonate. Because these numbers are part of the same chemistry panel, changes in one can influence the final result and its clinical significance.
At a basic level, the anion gap reflects the difference between the main positively charged and negatively charged ions in the blood. This makes it a useful diagnostic clue when assessing an unexpected result on a blood test. It can help identify whether a patient may have a hidden acid-base problem, such as metabolic acidosis, or whether the issue is better explained by a change in serum levels of proteins or a possible measurement error.
Most often, clinicians look at sodium, chloride, and bicarbonate together on the basic metabolic panel. These values are the backbone of many routine lab reviews. If sodium is low, the anion gap can seem different even when the underlying chemistry has not changed much. That is why understanding the formula matters before drawing conclusions about the normal range or deciding whether an abnormal value is meaningful.
How an Anion Gap Calculator Functions
An Anion Gap Calculator is a helpful utility that does the same calculation clinicians use when checking lab values. It combines the available serum bicarbonate, sodium, and chloride values to estimate the gap. Some calculators also ask for https://jsbin.com/mumiwesuju albumin or serum albumin because low protein levels can cause the result look falsely low and may need albumin correction.
The calculator is beneficial because it turns raw lab values into an reading aid. Rather than looking at sodium or chloride alone, it helps show how the numbers work together. This improves result accuracy when evaluating an unexpected result and gives a clearer picture of the patient’s electrolyte balance.
In practical use, the calculator supports clinicians in distinguishing whether the pattern points toward a high anion gap or a low anion gap. A high value may suggest excess unmeasured acids, while a low value may point to low albumin, a lab artifact, or less common causes such as paraproteins. The calculator does not replace judgment, but it aids faster, more structured lab interpretation.
Because the anion gap is calculated from routine chemistry data, even small shifts in sodium, chloride, or bicarbonate can change the outcome. That is why the calculator should always be used with the rest of the panel and the patient’s overall picture, not in isolation.
Can Reduced Sodium Alter the Anion Gap?
Indeed, hyponatremia can influence the anion gap, but the connection is rarely simple. Since sodium is part of the formula, a lower sodium value can alter the calculated result. However, a low sodium level does not automatically mean the anion gap is truly abnormal. The result may reflect the formula itself, the underlying cause of the sodium change, or a measurement error.
From a chemistry standpoint, the body maintains electroneutrality, meaning total positive and negative charges stay balanced. The anion gap is a way of estimating the portion of that balance not directly captured by the measured ions. If sodium falls, the calculation can shift, but whether that shift matters depends on the full lab pattern and clinical context.
For example, if sodium is low because of fluid imbalance or a dilutional state, the gap may appear lower without a true change in acid-base status. If chloride or bicarbonate also changes, the effect may be more obvious. This is why clinicians should not interpret sodium in isolation. They use the entire panel to decide whether the result reflects a real disorder or a misleading number.
Low sodium can also coexist with conditions that cause a truly abnormal anion gap. In that setting, the sodium change is not the primary driver of the gap, but it may complicate the lab interpretation. The question is not simply whether sodium is low, but whether the low sodium is changing the calculation enough to obscure the underlying cause.
Frequent Causes for Low Sodium and an Abnormal Anion Gap
Hyponatremia and an unusual anion gap often show up together because the same illness can influence fluid status, kidney handling of electrolytes, and acid production. One typical reason is dehydration. Although dehydration is often associated with concentrated labs, severe fluid loss can alter sodium and other values in ways that make interpretation complicated, especially if bicarbonate also changes.
Kidney disease is another important cause. If the kidneys cannot remove acids efficiently, the body may develop metabolic acidosis. In that setting, the anion gap may rise because unmeasured acids collect. Kidney dysfunction can also affect sodium regulation, making the lab pattern harder to interpret.
SIADH, or syndrome of inappropriate antidiuretic hormone secretion, is a common cause of hyponatremia. In SIADH, water retention dilutes sodium, and the anion gap may look unusual depending on the rest of the chemistry panel. The anion gap itself may not be the main issue, but it can still help detect whether another acid-base disorder is present.
Some patients with low sodium and abnormal acid-base findings have a mixed problem. For example:
- Hyponatremia with low bicarbonate may suggest a metabolic process that needs closer review. Hyponatremia with elevated chloride may lower the anion gap or point away from a high-gap disorder. Kidney disease can contribute to both sodium imbalance and metabolic acidosis.
The key point is that low sodium may be a clue, not the diagnosis itself. A careful review of electrolytes, serum bicarbonate, and other lab values is needed to determine the real diagnostic clue behind the pattern.
Low Anion Gap vs Increased Anion Gap
A low anion gap and a high anion gap suggest very different causes. A high anion gap usually indicates too much acids in the blood, while a low anion gap often reflects decreased albumin, a lab issue, or uncommon disorders. That difference matters because the treatment approach depends on the magnitude of the change.
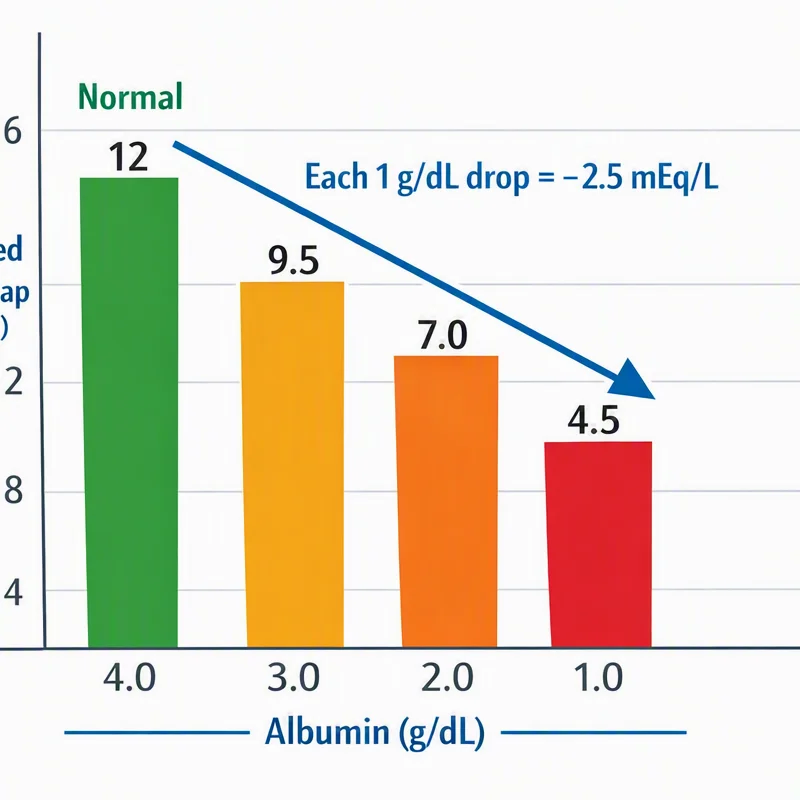
Albumin is one of the most important reasons a low anion gap can occur. Because albumin carries negative charge, low albumin can reduce the gap even when sodium, chloride, and bicarbonate are otherwise stable. This is why albumin correction is often needed. A corrected anion gap may show that the result is less concerning than it first appeared.
By contrast, a high anion gap often appears in conditions such as lactic acidosis and ketoacidosis. In lactic acidosis, the body retains lactate due to poor oxygen delivery or impaired metabolism. In ketoacidosis, ketones build up when the body uses fat for fuel. Both conditions can produce a high anion gap metabolic pattern that requires prompt attention.
Paraproteinemia can also lead to a low anion gap. Abnormal proteins in the blood may change the charge balance enough to affect the calculation. This is less frequent than low albumin, but it is clinically important when the result does not fit the rest of the labs.
Thinking in terms of low versus high anion gap helps refine the differential. It also keeps the clinician focused on the reference range, the surrounding chemistry, and the true clinical significance of the result rather than the number alone.
If a Reduced Anion Gap Is a Laboratory Artifact
Not every lower anion gap reflects a medical problem. At times the result is a lab error or other lab artifact. For this reason result review should include the possibility of a specimen issue, especially when the number does not fit the patient’s symptoms or other findings.
One especially important artifacts is pseudohyponatremia. In this case, the measured sodium may appear lower than it really is because of unusual sample composition, such as extreme protein or lipid levels. If sodium is falsely low, the calculated anion gap may also appear misleading. This can produce a unclear pattern unless the sample is repeated or tested with a different method.
One more common measure is testing again. If the outcome is unexpected, doing again the blood test helps determine whether the issue is actual or due to chance variation, collection problems, or instrument-related problems. This is especially vital when the lab pattern is not consistent with the patient’s condition.
When sodium, chloride, or bicarbonate do not fit the clinical picture, first consider whether the value is consistent before assuming a genuine acid-base problem.
A decreased anion gap resulting from an error is typically resolved when the sample is rechecked. That is why clinicians pay close attention to measurement error and how the specimen was collected, processed, and evaluated.
Ways Clinicians Interpret the Result
Clinicians rarely read the anion gap on its own. They look at the basic metabolic panel first, then add an arterial blood gas if necessary to understand the acid-base status in greater detail. These tests together give a clearer view of the patient’s biochemistry and respiratory function.
Assessment often commences with reviewing sodium, chloride, bicarbonate, and serum albumin. If albumin is low, the anion gap may need albumin correction prior to interpretation. This is essential because a corrected anion gap may change the interpretation from abnormal to within normal range.
The next stage is putting the result into clinical context. Is the patient sick, dehydrated, confused, short of breath, or demonstrating kidney dysfunction? Are there symptoms that suggest lactic acidosis or ketoacidosis? Does the pattern fit SIADH, or is there evidence of paraproteinemia? These considerations help determine whether the number represents a true disorder or a transient lab finding.
Clinicians also review the result with prior labs when available. A sudden change may be more important than a mildly abnormal value that has remained stable. This strategy helps identify the underlying cause and supports better decision-making around further testing, treatment, or observation.
In short, the anion gap is a calculated value, but its interpretation is a clinical process. The best interpretation guide combines the calculator result with the patient’s symptoms, lab trend, and possible diagnosis.
When It’s Time for Medical Evaluation
Low sodium and an abnormal anion gap deserve medical evaluation when they are associated with worrisome symptoms or when the result is severe. Some mild changes can be followed over time, but significant abnormalities can indicate a serious disorder that needs prompt attention.
Special concern comes with severe hyponatremia. If sodium is very low, the brain can be affected, leading to confusion, headache, nausea, weakness, or more serious neurologic symptoms. These findings should not be ignored, especially if the patient also has an abnormal anion gap or signs of metabolic illness.
Seek urgent emergency care if abnormal labs occur along with fainting, seizures, severe confusion, trouble breathing, chest pain, or marked decline in alertness. These may indicate a life-threatening electrolyte or acid-base disturbance.
Even without symptoms, a low anion gap may still warrant follow-up, especially if the result is persistent or paired with low albumin, kidney disease, or suspected paraproteinemia. Even if the cause is ultimately a lab artifact, confirmation matters because it prevents missed diagnoses and avoids unnecessary treatment.
The most prudent approach is to treat the Anion Gap Calculator as a guide, not a diagnosis on its own. If the result is unexpected, repeat the labs, review the basic metabolic panel, and discuss the findings with a clinician who can interpret them in context.
FAQ
Can sodium being low reduce the anion gap?
Yes, it can. Since sodium is included in the anion gap calculation, low sodium can lower the calculated value. However, the result may also reflect the underlying condition causing the sodium change or a lab artifact, so it should be interpreted with chloride, bicarbonate, and serum albumin.
Does hyponatremia cause a low anion gap?
Hyponatremia may play a role in a low anion gap, but it does not always cause one by itself. The bigger question is why the sodium is low and whether other values, such as chloride and bicarbonate, support a true acid-base disorder.
What is the leading cause of a low anion gap?
Reduced albumin levels is one of the leading causes of a low anion gap. This is why albumin correction is crucial. After that, lab artifact and measurement issues are also frequent explanations, especially when the result does not fit the clinical picture.
Can a low anion gap be due to a lab error?
Yes. A low anion gap can result from lab error, specimen issue, or pseudohyponatremia. Repeat testing is often the preferred first step when the value is surprising or not aligned with other lab findings.
When should I worry about abnormal sodium and anion gap results?
You should seek medical evaluation if abnormal sodium and anion gap results occur with symptoms such as disorientation, severe weakness, vomiting, shortness of breath, or signs of severe hyponatremia. Emergency care is critical if there are neurologic symptoms or a fast-progressing condition.