What the Anion Gap Indicates in Acidemia
The anion gap is a practical way to assess acidemia and refine the probable cause of metabolic acidosis. It shows the gap between commonly measured serum electrolytes and guides clinicians understand whether unmeasured acids may be present in the blood. In simple terms, the anion gap is a clue about the body’s acid-base balance and whether the problem is being driven by acid accumulation, bicarbonate loss, or another disorder.
Acidemia means the blood pH is below normal. That does not always mean the primary problem is metabolic, but a low pH often prompts an acid-base analysis. The anion gap is especially useful because it can help separate high anion gap metabolic acidosis from normal anion gap metabolic acidosis. That distinction changes the differential diagnosis, the urgency of evaluation, and the type of follow-up testing that may be needed.
At a basic level, the anion gap compares positively charged ions with negatively charged ions in a standard chemistry profile. A elevated gap suggests extra unmeasured anions, such as lactate or ketones. A normal gap may suggest a bicarbonate loss problem instead. Because of that, the anion gap is not just a number; it is part of the overall interpretation of laboratory values in context with symptoms, severity, and other results.
How to Utilize an Anion Gap Calculator
An Anion Gap Calculator generally uses three core values: serum sodium, serum chloride, and serum bicarbonate. A few calculators also let you add albumin so the result can be adjusted for low protein levels. This is helpful because the raw value alone may underestimate the true difference when hypoalbuminemia is present.
The usual process is easy:
- Input the sodium value from the chemistry panel. Type in the chloride value. Input the bicarbonate value. Examine the calculated anion gap and compare it with the reference range. If albumin is low, calculate the corrected anion gap.
The calculator is most valuable when used for evaluation, not in isolation. For example, a mildly elevated result may be less worrisome if the clinical picture is stable and the patient’s symptoms do not suggest a serious disorder. On the other hand, a markedly elevated value with severe symptoms, abnormal vital signs, or worsening laboratory values needs prompt attention.
Using the calculator also supports more rapid screening for hidden causes of acidosis. A chemistry panel can show the raw numbers, but the calculated difference helps highlight the pattern. This makes it easier to decide whether the issue is more consistent with increased acid production, impaired acid excretion, or a bicarbonate-losing process.
Ion Gap Equation and Normal Ranges
The standard anion gap formula reads:
Anion gap = sodium − (chloride + bicarbonate)
Some laboratories follow slightly different calculations or incorporate potassium, but the sodium-based version is the most frequent in standard practice. Because reporting methods vary, the expected normal anion gap depends on the laboratory method and the local electrolyte panel. For that reason, the correct reference range is the one used by the reporting lab, not a universal number.
In clinical practice, https://anion-gap-values163.brightsora.com/posts/anion-gap-calculator-in-pediatrics-how-to-assess-and-interpret-results a normal result does not automatically exclude a disorder, and an elevated result does not diagnose a specific cause by itself. The calculation is a clue that must be paired with the rest of the acid-base analysis. A higher-than-expected result suggests an accumulation of unmeasured anions, while a normal result can still be seen in serious illness if bicarbonate loss is being offset by chloride retention.
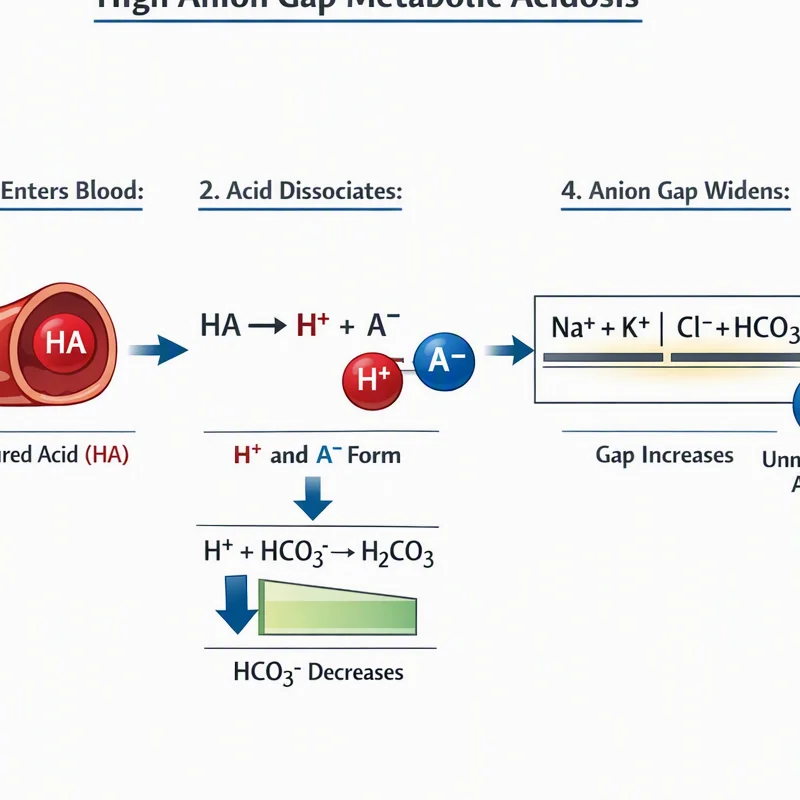
It also helps to remember that laboratory values may shift during illness or treatment. A changing anion gap can be more informative than a single number, especially when the patient’s condition is evolving. Serial analysis can reveal whether the cause of metabolic acidosis is improving, worsening, or being masked by another process.
Correcting Albumin and Its Importance
Albumin is a important unmeasured anion in blood. When albumin is reduced, the measured anion gap may look falsely low even if clinically relevant acid accumulation is occurring. This is why hypoalbuminemia can obscure the true picture and why the corrected anion gap is often preferable than the unadjusted value.
Albumin correction refines acid-base interpretation by accounting for the fact that low albumin lowers the baseline gap. Without correction, a patient with important acid accumulation might be incorrectly labeled as having a normal result. That can postpone recognition of serious disease and reduce the accuracy of the differential diagnosis.
A corrected value is especially helpful when the clinical context points to acidosis but the initial anion gap is not strikingly abnormal. In those cases, the raw chemistry may be misleading. Correcting for albumin helps bring back the gap closer to what it would be with normal protein levels, making the analysis more accurate.
In practice, the correction is most beneficial when evaluating critically ill patients, those with chronic illness, or anyone with low albumin on laboratory testing. It can alter the interpretation from apparently normal to clearly abnormal, which may point toward high-gap causes. The corrected result should still be considered alongside symptoms, other laboratory values, and the full acid-base picture.
Elevated Anion Gap vs Normal Anion Gap Acidosis
Elevated anion gap metabolic acidosis happens when extra acids elevate the number of unmeasured anions in the blood. Frequent examples include lactate, ketones, and retained organic acids. The gap rises because bicarbonate is used up buffering those acids, while chloride does not rise enough to keep the gap normal.
Normal anion gap acidosis, also called chloride-associated metabolic acidosis, commonly occurs when bicarbonate is lost and chloride rises to maintain electroneutrality. The anion gap stays within the expected range even though the patient still has metabolic acidosis. This pattern is important because the underlying cause and treatment are different from those of a high-gap disorder.
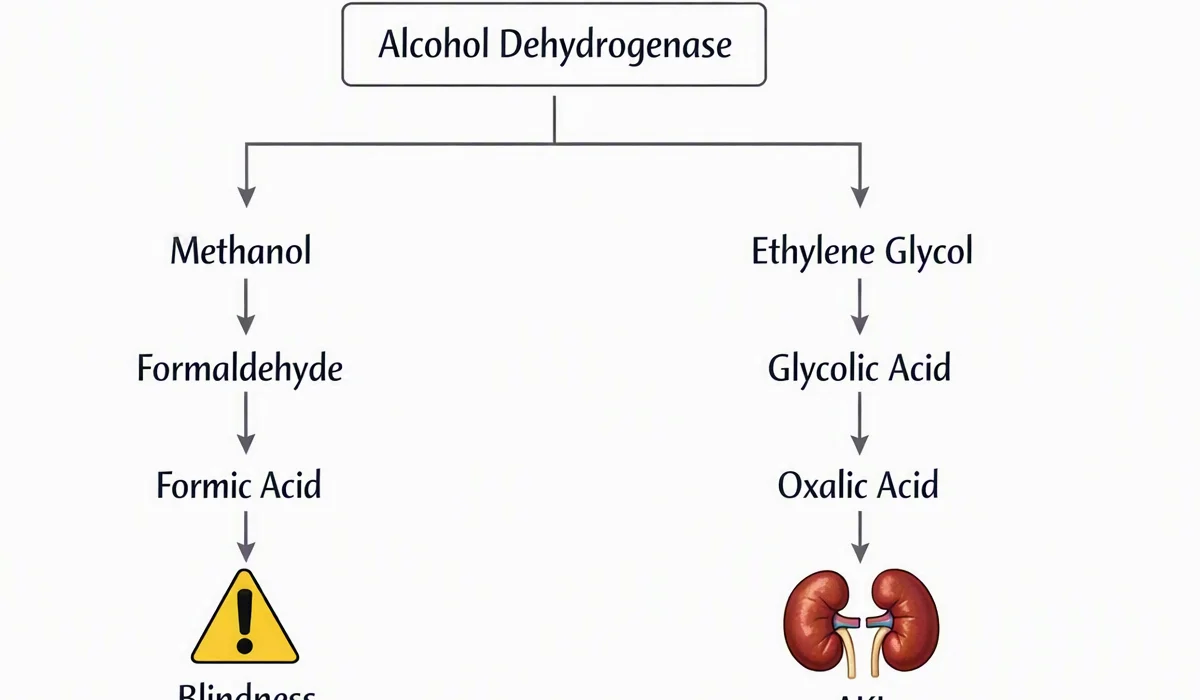
Lactic acidosis is one of the key high-gap causes because it may indicate poor tissue oxygen delivery, shock, sepsis, medication effects, or other serious illness. The presence of renal failure can also raise the gap because impaired kidney function reduces acid excretion and allows unmeasured acids to accumulate.
Pattern recognition matters. If the gap is high, the next question is usually what unmeasured acid is responsible. If the gap is normal, the focus shifts to bicarbonate loss, chloride excess, or renal tubular disorders. In both cases, the calculator supports diagnosis by organizing the laboratory picture into a more usable framework.
Common Causes of Acidemia by Anion Gap
Several frequent issues can help explain acidemia, and the anion gap aids sort them into types.
- Ketoacidosis: Observed when ketone generation increases and acids build up, often with insulin lack, starvation, or prolonged alcohol use. Salicylate toxicity: May produce mixed acid-base changes and often requires careful assessment of the full laboratory pattern. Diarrhea: A regular cause of bicarbonate depletion, usually linked to normal anion gap metabolic acidosis. Renal tubular acidosis: A kidney disorder that disrupts acid regulation and often results in a normal gap picture. Renal failure: Can lead to retention of acids and promote high anion gap metabolic acidosis. Lactic acidosis: Often associated with hypoperfusion, infection, medication effects, or severe physiologic stress.
The symptom profile can also guide interpretation. For example, vomiting, dehydration, infection, altered mental status, rapid breathing, or abdominal symptoms may point toward a specific cause. The calculator does not substitute for clinical judgment, but it can rapidly highlight the most likely group of disorder.
In practical analysis, more than one process may be present. A patient may have both lactic acidosis and diarrhea, or ketoacidosis with renal impairment. That is why the anion gap is best used as part of a broader workup rather than as a stand-alone answer.
Stepwise Assessment of Acid–base Disorders
When acidemia is suspected, a structured approach is more reliable than examining one value alone. An arterial blood gas is commonly used to assess pH and respiratory compensation, while a venous blood gas may also provide useful information in many settings. In combination with the chemistry panel, these tests help identify the disorder.
A practical stepwise approach includes the following:
- Check the pH to verify acidemia. Assess PaCO2 to see whether the respiratory system is compensating or contributing to the problem. Review bicarbonate to determine whether the primary issue is metabolic. Calculate the anion gap from the electrolyte panel. Evaluate whether the gap is elevated, normal, or corrected for albumin. Apply the pattern to guide the next diagnostic question.
This sequence helps distinguish respiratory from metabolic disorders and shows whether the abnormality is acute, compensated, or mixed. A low pH with low bicarbonate usually suggests metabolic acidosis, but the PaCO2 helps determine whether respiratory compensation is appropriate. If PaCO2 is higher than expected, a mixed disorder may be present.
The strength of this approach is that it links calculation to interpretation. A result that seems small in isolation may still be important if the pH is low and the clinical context suggests a serious cause. Likewise, an elevated gap may need confirmation with repeat testing if the sample quality or timing is uncertain.
When to Recheck Labs or Get emergency care
Some cases need prompt reassessment because acid-base problems can worsen quickly. Severe acidemia is especially concerning when it occurs with confusion or reduced alertness, trouble breathing, unstable vital signs, or signs of shock. When this happens, immediate medical evaluation is appropriate.
Retesting may be needed when the initial results do not fit the clinical picture, when the patient is declining, or when treatment has begun and response needs to be measured. Rechecking electrolyte abnormalities can show whether the bicarbonate, chloride, or sodium values are shifting in the expected direction.
Blood lactate testing is often important when high-gap acidosis is suspected, especially if there is concern for poor perfusion or infection. Rising lactate can indicate ongoing tissue stress and may signal the need for urgent intervention. Other high-risk results on the lab report, such as extreme potassium abnormalities or very low bicarbonate, also increase risk and should not be ignored.
If the patient has worsening symptoms, confusion, chest pain, rapid breathing, profound weakness, or dehydration, urgent evaluation is warranted. The calculator is useful for initial review and interpretation, but it should never delay care when the clinical presentation is concerning.
FAQ
What is an anion gap calculator used for in acidemia?
Anion Gap Calculator is used to estimate the difference between measured cations and anions, helping identify the likely cause of acidemia. It supports interpretation of metabolic acidosis by showing whether the pattern is more consistent with a high-gap process such as lactate or ketones, or a normal-gap process such as bicarbonate loss.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
The common calculation is sodium minus the sum of chloride and bicarbonate. In other words, anion gap = serum sodium − (serum chloride + serum bicarbonate). The result should then be compared with the lab’s reference range and interpreted in the context of the electrolyte panel and acid-base balance.
Why does the albumin affect the anion gap?
Albumin influences the anion gap because it is a key nonmeasured anion in the blood. When albumin is low, the measured gap may be falsely decreased. Albumin correction supports produce a corrected anion gap that better reflects the true acid-base interpretation, especially in hypoalbuminemia.
What does a high anion gap mean?
A high anion gap usually means there are more unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and salicylate toxicity. A high result does not identify the cause by itself, but it strongly indicates a high anion gap metabolic acidosis that needs further evaluation.
Can acidemia occur with a normal anion gap?
Absolutely. Acidemia can occur with a normal anion gap when bicarbonate is lost and chloride rises to compensate, such as with diarrhea or renal tubular acidosis. This is called normal anion gap metabolic acidosis, and it is an important pattern because it points to a different diagnosis and management approach than high-gap acidosis.