What Is the Anion Gap?
The anion gap is a computed value used to check acid-base balance and recognize certain types of metabolic acidosis. It comes from a standard look at the body’s major electrolytes, especially the measured ions on routine blood chemistry analysis. In simple terms, the anion gap compares positively charged and negatively charged particles in the blood to suggest whether there are extra unmeasured ions present.
This is helpful because normal physiology keeps these charges in balance. When that balance changes, it may suggest an electrolyte imbalance or a broader metabolic disturbance. The anion gap is not a diagnosis by itself. Instead, it is a screening tool that supports diagnostic interpretation in the right clinical context.
Changes in the anion gap can point to shifts in acid-base status, especially when evaluating a patient with symptoms or abnormal lab values. A high result can suggest accumulation of acids, while a low result is less common and may reflect protein changes, calculation issues, or a true shift in blood chemistry.
How to Use an Anion Gap Calculator
An anion gap calculator based on a BMP, or basic metabolic panel, uses standard lab results to calculate the gap promptly. The standard inputs are sodium, chloride, and bicarbonate. On many reports, bicarbonate may appear as carbon dioxide, which is used as a proxy for serum bicarbonate in routine testing.
To use the calculator, enter the values from the BMP. The tool follows the formula and returns a calculated value that can be compared with the expected reference range. Because the calculation depends on serum concentrations, accuracy depends on correct entry of the serum sodium, serum chloride, and serum bicarbonate values.
Below is the basic procedure:
- Find the sodium value on the BMP. Find the chloride value on the same panel. Identify the bicarbonate or carbon dioxide value. Run the calculator to compute the anion gap. Compare the result with the expected normal range and interpret it alongside symptoms and other lab findings.
A calculator can streamline interpretation, but it does not substitute for clinical judgment. A result that seems abnormal may still be appropriate depending on the overall picture, including medications, hydration status, and other lab results.
Anion Gap Calculation and Expected Range
The traditional anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Because the calculation is based on measured ions, it estimates the balance between major cations and anions in blood. That difference represents mostly unmeasured ions, including proteins, phosphates, sulfate, and organic acids. These components help explain why the result is not zero in normal blood.
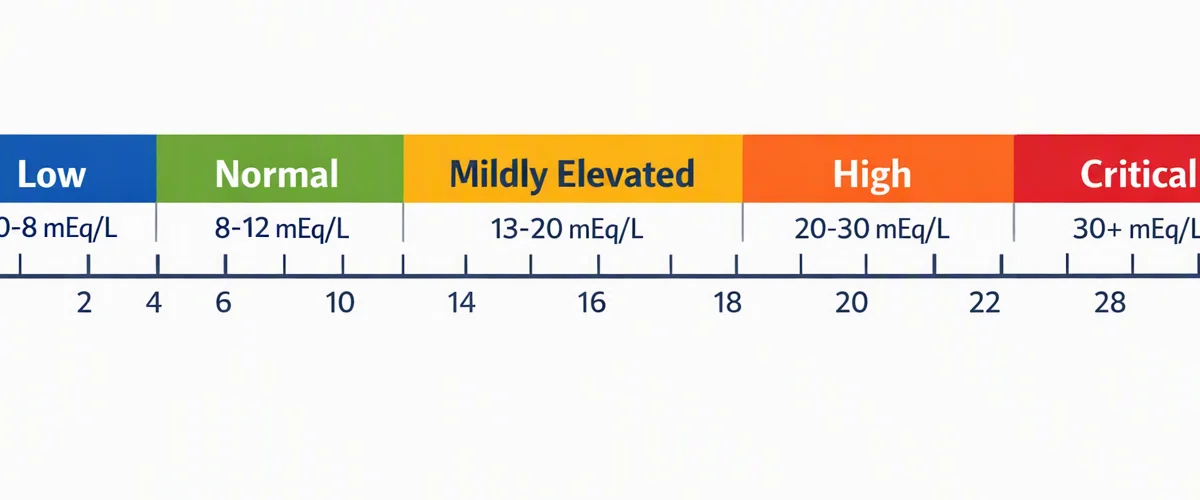
The typical normal range depends on the lab method and whether potassium is included. Many modern labs use a reference range that is narrower than older ranges, and the exact cutoff can vary by analyzer. This is why it is important to interpret the calculated value using the lab’s own reference range rather than assuming one universal number.
Albumin matters because it is a principal negatively charged protein in the blood. If albumin is low, the measured gap may look artificially low even if the underlying acid-base state is not normal. In those cases, clinicians may use a corrected anion gap with albumin correction to better reflect the real state of the blood chemistry.
The anion gap is a helpful way to identify whether there may be extra acids or other unmeasured ions contributing to an abnormal result. It is especially useful when interpreting metabolic acidosis and deciding whether additional workup is needed.

What a Increased Anion Gap Indicates
A high anion gap often suggests that excess acids are present in the blood. This finding is commonly seen in metabolic acidosis, where the body has built up acids or struggled to clear them effectively. The result is not limited to one disease, but it often points toward important conditions that need prompt attention.
One major cause is lactic acidosis, which can occur when tissues do not get enough oxygen or when cells are under significant stress. Another important cause is ketoacidosis, which can develop when the body produces excessive amounts of ketones, often during insulin deficiency, prolonged fasting, or severe illness. Both conditions increase acid levels and can raise the calculated value.
Renal failure can also cause a high result because the kidneys are less able to clear acids and other waste products. As those substances accumulate, the blood chemistry changes and the anion gap may rise. This pattern can be seen with uremia, where retained metabolic products contribute to acid-base imbalance.
When the result is high, the number alone does not reveal the cause. The best interpretation comes from combining the anion gap with symptoms, other lab values, and the overall clinical context. For example, a modestly increased gap in one setting may be less urgent than the same value in a person with deep breathing, confusion, or dehydration.
What Exactly a Low Anion Gap Means
A low anion gap is uncommon than an elevated one and can be caused by multiple issues. One of the key is hypoalbuminemia, because low albumin lowers the amount of negatively charged protein in the blood. When albumin falls, the calculated value may also decrease, even if the rest of the electrolytes seem normal.
Another cause is paraproteinemia, where abnormal proteins in the blood disturb the balance of measured and unmeasured charges. This may happen in specific plasma cell disorders and can produce an unexpectedly low result. In these situations, the anion gap is not simply a number issue; it may be a clue to a broader medical condition.
Lab error is also a typical explanation for a low result. Mistakes in specimen handling, transcription, analyzer performance, or unit entry can all distort the calculation. If the value does not match the rest of the picture, repeating the BMP or reviewing the original sample may be warranted.
Because a low result may reflect protein changes, measurement issues, or a real physiologic shift, it should not be ignored. It deserves closer consideration in the same way a high result does, especially if symptoms or other abnormal findings are present.
Basic Metabolic Panel vs Comprehensive Metabolic Panel for Anion Gap Calculation
Both the BMP and CMP can be used in anion gap assessment, but they are not equivalent. A basic metabolic panel provides the key electrolytes needed for the measurement: sodium, chloride, and bicarbonate or carbon dioxide. This makes the BMP the most direct and common source for an anion gap calculator.
The CMP, or chemistry panel, offers the same core electrolytes plus additional tests, including albumin and liver-related markers. This added information can enhance interpretation because albumin helps determine whether a corrected anion gap should be considered.
In practice, the electrolytes panel on a BMP is adequate to calculate the raw gap, but the CMP adds important context. If albumin is low, a raw number may downplay the true abnormality. That is why the distinction between BMP and CMP matters: the BMP provides the value, while the CMP may help clarify the result.
For routine screening, the BMP is often adequate. For deeper interpretation, especially in suspected acid-base disorders, the CMP can provide a more comprehensive view of the patient’s blood chemistry.
Common Causes of Abnormal Anion Gap
An abnormal value can stem from many acid-base disorders, and the pattern matters. A high value usually suggests excess acids or accumulated acids, while a low value often reflects protein shifts or measurement problems. Knowing the cause helps direct next steps.
Some frequent causes of a high result are:
- Lactic acidosis from poor oxygen delivery, shock, or severe illness Ketoacidosis from insulin deficiency, fasting, or other metabolic stress Renal failure with buildup of acid and waste products Uremia due to impaired clearance of metabolic byproducts Toxins that generate or create acids
Salicylates are a classic toxin-related cause of abnormal acid-base findings. They can produce complex changes in breathing and metabolism and may result in a high gap. Other toxins can also alter the balance of measured and unmeasured substances in the blood.
For a low result, the most common contributors are hypoalbuminemia, paraproteinemia, and lab error. In some cases, medications or unusual electrolyte patterns may also contribute. The key is to https://anion-gap-results067.tearosediner.net/revised-anion-gap-calculator-and-how-to-interpret-it interpret the number as part of the larger diagnostic picture rather than as a stand-alone finding.
When to Pursue Medical Review
If you have an abnormal result on a blood test, the best next step depends on the number, your symptoms, and the reason the test was ordered. A slightly abnormal value may be reviewed at a subsequent visit, but a significantly abnormal result with concerning symptoms should be assessed quickly by a clinician.
Seek urgent emergency care if an abnormal result is paired with severe vomiting, rapid breathing, confusion, fainting, chest pain, marked weakness, or signs of dehydration. These symptoms can appear with serious metabolic acidosis or other acute metabolic problems.
Because the anion gap is a calculated value, it should be interpreted alongside the rest of the lab panel and the clinical presentation. A person with high anion gap acidosis may need immediate evaluation, while a person with a low anion gap may need repeat testing, albumin review, or assessment for protein abnormalities.
If you are unsure what your result means, bring the report to a clinician for review. The most useful interpretation combines the calculator result with your history, medications, physical findings, and the full set of lab values.
Frequently Asked Questions
How do you find the anion gap from a BMP?
Use the values for sodium, chloride, and bicarbonate from the BMP. The standard formula is sodium minus the sum of chloride and bicarbonate. Many anion gap calculator tools use this same method, and some reports list bicarbonate as carbon dioxide. The result is then compared with the lab’s normal range for interpretation.
What counts as a normal anion gap range?
The normal range varies by laboratory and analyzer, so there is not one universal cutoff. Different labs may report slightly different ranges depending on their methods. The safest approach is to compare the calculated value with the reference interval provided by the lab that performed the BMP. Albumin level and clinical context can also affect interpretation.
Why can the anion gap to remain high even if bicarbonate is only mildly low?
A elevated anion gap can appear prior to bicarbonate falls dramatically because the gap reflects build-up of unmeasured ions and acids. In initial or mixed disorders, the bicarbonate may be only mildly low while lactic acidosis, ketoacidosis, or a different acid load is already present. This is why the anion gap is useful for detecting metabolic acidosis that may not yet be obvious from bicarbonate alone.
Can I determine an anion gap without albumin?
Absolutely, you can calculate the raw anion gap without albumin because the standard BMP provides the needed electrolytes. However, albumin is important for interpretation because low albumin can produce a deceptively low result. If hypoalbuminemia is present or suspected, a corrected anion gap with albumin correction may be more informative.
What should I do if my anion gap is abnormal?
If your result is abnormal, go over it with a clinician who can interpret it in the full clinical context. A repeat blood test may be needed if lab error is possible, and additional testing may be ordered to look for metabolic acidosis, renal failure, salicylates, uremia, or other causes. If you also have concerning symptoms, especially breathing changes, confusion, or severe weakness, seek emergency care.