What exactly is the Anion Gap?
The anion gap is a calculated value used to assess electrolyte balance and overall acid-base status in adults. It examines the major measured ions in blood chemistry, especially sodium and chloride, and assists clinicians in estimating the amount of unmeasured anions in the bloodstream.
Although the number is straightforward, its meaning is wide-ranging. A change in the anion gap can point to a shift in serum electrolytes, an increase in systemic acid load, or a problem that affects how the body maintains acid-base balance. Because it reflects the interaction between several lab values, the anion gap is a valuable diagnostic tool rather than a standalone diagnosis.
In adult care, the anion gap is often reviewed alongside the electrolyte panel, bicarbonate concentration, and other blood chemistry results. It can aid in identifying metabolic acidosis, especially when the cause is not immediately obvious. When interpreted correctly, it offers a quick clue to whether acid has accumulated in the body or whether certain proteins and ions are affecting the measurement.
How to Work With an Anion Gap Calculator
An anion gap calculator helps to carry out the calculation rapid and consistent. You provide the numbers for serum sodium, serum chloride, and serum bicarbonate, and the calculator returns the anion gap. This is very helpful when reviewing multiple lab values or when you want a rapid check during clinical interpretation.
For using the calculator properly, be sure you are entering the same type of values the formula expects. Most calculators use concentrations from a standard blood chemistry panel. If your lab report lists a bicarbonate or total CO2 value, check that it is the intended value for the calculation. Even a small input mismatch can change the result enough to affect interpretation.
- Enter the serum sodium value exactly as reported. Enter the serum chloride value from the same blood draw. Provide the serum bicarbonate value from the same panel. Review the output in the context of the patient’s symptoms and other lab findings.
An anion gap calculator is best viewed as a clinical interpretation aid. It does not replace assessment of the patient’s history, medication use, renal function, or possible toxic ingestion. It provides a number, but the number only becomes useful when matched to the broader picture.
Anion Gap Formula and Calculation Steps
The usual anion gap formula is:
Na minus Cl minus HCO3
In clinical terms, that means taking away serum chloride and serum bicarbonate from serum sodium. Certain labs and calculators show the equation as Na minus Cl with bicarbonate factored in the final step, but the principle is the same: the result estimates the gap between measured cations and measured anions.
Here is the standard calculation workflow:
- Begin by starting with the serum sodium value. Subtract the serum chloride value. Deduct the serum bicarbonate value. The result is the anion gap.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. That number may sit within a normal adult range depending on the lab’s reference interval.
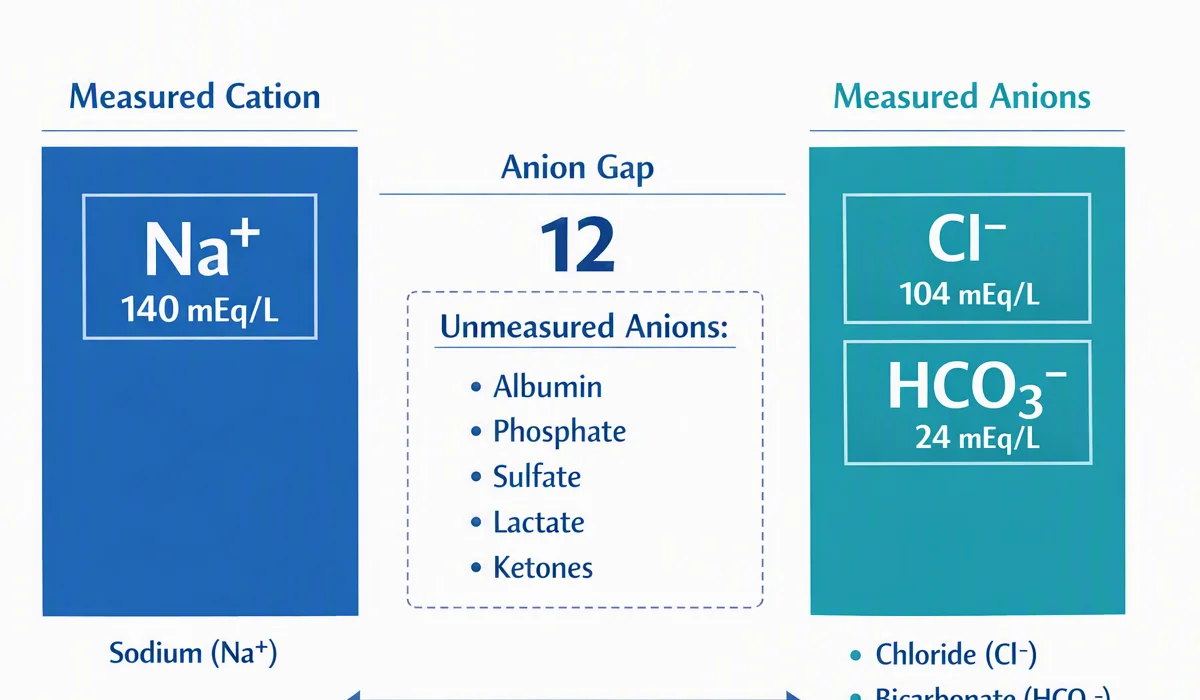
One reason the calculation matters is that it shows the presence of unmeasured anions such as proteins, phosphate, sulfate, organic acids, and other components not directly listed in the routine electrolyte panel. Since albumin is a major unmeasured anion, changes in albumin can significantly affect the result. That is why some clinicians also consider an albumin-adjusted or corrected value.
Expected Anion Gap Range in Adults
The usual anion gap range in adults varies with the laboratory method and the analyzer used. There is not one universal value, because lab values can vary based on calibration, measurement approach, and local reporting practices. For that reason, the best reference interval is the one provided by the lab that performed the adult blood test.
In many settings, the normal anion gap is considered fairly narrow, but it may differ enough between labs that a borderline result should be interpreted carefully. A value that is normal in one system may be a little abnormal in another. This is why the reported reference interval should always be checked before drawing conclusions.
When reviewing a result, focus on whether the value is meaningfully different from the expected range rather than whether it is only a little above or below the cutoff. Small differences may reflect typical biological variation, test variation, or a mild shift in electrolyte balance.
Because the anion gap is influenced by albumin, a person with low albumin may appear to have a “normal” or even low value despite a clinically important problem. That is one reason the number should never be interpreted by itself.
High Anion Gap: Frequent Causes
An elevated anion gap may indicate high anion gap metabolic acidosis, an example of metabolic acidosis in which acidic substances collect and raise the amount of unmeasured anions. This finding matters because it may signal a serious underlying disorder that needs rapid attention.
Typical causes include lactic acidosis, ketoacidosis, and renal failure. All of these may cause a systemic acid load that drives up the anion gap.
- Lactic acidosis: Frequently related to tissue hypoperfusion, sepsis, hypoxia, or other conditions that increase lactate elevation. Ketoacidosis: Occurs with uncontrolled diabetes, starvation, alcohol use, or other states of ketone accumulation. Renal failure: Poor elimination of acids and reduced renal function can allow acids to build up.
Other reasons for a high value may involve certain toxic ingestion scenarios, which can also alter the osmolar gap. That is why a high anion gap should trigger a broader search for the source of acid accumulation rather than ending the evaluation.
In clinical practice, a high value is usually interpreted alongside symptoms, vital signs, medication history, and an arterial blood gas. The goal is not just to name the abnormality but to identify the process driving it.
Reduced Anion Gap: Likely Reasons
A low anion gap is rarer than a high one, but it can still be important clinically. The most common explanations include hypoalbuminemia, multiple myeloma, lithium toxicity, and laboratory error.
Hypoalbuminemia is the most frequent reason because albumin is a major unmeasured anion. When albumin falls, the calculated gap may also fall even if acid-base status has not shifted much. This makes the finding easy to overlook unless the clinician considers protein levels and overall clinical context.
Multiple myeloma can lower the anion gap because abnormal positively charged proteins may alter the balance of measured and unmeasured ions. In some cases, the anion gap becomes a clue that prompts further workup for a plasma cell disorder.
Lithium toxicity may also produce a low value because lithium acts as an unmeasured cation. If a patient is taking lithium and the result is unexpectedly low, medication review becomes necessary.
https://anion-gap-tool058.publishlane.com/posts/what-means-the-anion-gap-in-respiratory-alkalosisFinally, laboratory error or lab variation should always be considered. A single unexpected low result may reflect sample handling issues, instrument problems, or measurement error. Repeating the test is often the best first step when the result does not fit the rest of the picture.
Revised Anion Gap and Albumin Correction
Because albumin greatly influences the anion gap, many clinicians rely on albumin correction to obtain a corrected anion gap. This approach helps compensate for low serum albumin and gives a more precise view of acid-base balance.
Why this adjustment matters is simple: when albumin is low, the measured gap may miss the degree of acid disturbance. An albumin-adjusted result can show a hidden high anion gap that would otherwise be overlooked.
Even though different formulas are available, the general principle is that lower albumin heightens the likelihood of misjudging the true gap. In everyday interpretation, if serum albumin is reduced, the raw number should be viewed with caution and corrected when necessary.
This matters especially in patients with chronic illness, malnutrition, liver disease, inflammation, or other conditions associated with low albumin. In those settings, the corrected value often more closely represents the patient’s real biochemical state and allows more reliable clinical interpretation.
Interpreting Results in Medical Context
The anion gap is most helpful when paired with the rest of the clinical evaluation. An standalone number can be misleading, but a number paired with symptoms, exam findings, and additional labs can sharpen the diagnosis rapidly.
When the result is outside the normal range, review the arterial blood gas, bicarbonate level, and chloride level together. These values help determine whether the patient truly has metabolic acidosis, whether respiratory compensation is present, and whether chloride changes are contributing to the pattern.
A low bicarbonate level with an elevated anion gap strongly suggests metabolic acidosis. A low bicarbonate with a normal gap may suggest a different type of acid-base disorder. A high or low chloride level can also point toward dilutional effects, vomiting, diarrhea, renal tubular problems, or other disturbances in serum electrolytes.
Clinical interpretation should also account for medication use, fluid status, blood pressure, kidney function, and possible exposure to toxins. In other words, the anion gap is a indicator, not the final answer.
Limitations of the Anion Gap Calculator
Even a well-designed anion gap calculator has limitations. It depends on correct input, accurate lab reporting, and the assumption that the measured values are reliable. If any of these elements are off, the result may be misleading.
Measurement error can occur with any blood test. Small errors in sodium, chloride, or bicarbonate can shift the number enough to change interpretation, especially when the value is borderline.
Lab variation is another issue. Different analyzers and methods may produce slightly different results, which affects the reported normal anion gap range. This is why comparison with the local reference interval matters more than comparing numbers from different systems.
The calculator also does never determine each source of acid-base imbalance. Some people may have combined acid-base disorders, which can mask the expected pattern. In addition, the osmolar gap may be important when toxic alcohol exposure or another toxic ingestion is considered. The anion gap and osmolar gap can enhance each other, but they are not synonymous.
In the end, the calculator assists clinical decisions, but it does not take the place of clinical reasoning, repeat testing when needed, or broader diagnostic evaluation.
Frequently Asked Questions
What is an anion gap calculator used for in adults?
An anion gap calculator is used to efficiently calculate the anion gap from common blood chemistry values. In adults, it helps measure metabolic acidosis, recognize possible acid accumulation, and support the broader evaluation of electrolyte balance and acid-base status.
What is a normal anion gap range in adults?
The normal anion gap range in adults depends on the laboratory and analyzer used. Because laboratory values differ, the most accurate answer is the lab’s own reference interval. A result should always be interpreted in relation to that lab’s reported normal range.
What causes a high anion gap?
A high anion gap is commonly caused by high anion gap metabolic acidosis. Frequent causes include lactic acidosis, ketoacidosis, and renal failure. Toxic ingestion and other conditions that increase unmeasured anions can also elevate the value.
Why can albumin change the anion gap result?
Albumin is a major unmeasured anion, so changes in albumin affect the calculated result. When serum albumin is low, the anion gap may appear lower than expected. That is why albumin correction and the corrected anion gap are crucial in many adult patients.
Can one decreased anion gap be a marker of a serious condition?
Yes, it can. A low anion gap can occasionally point to an important problem such as hypoalbuminemia, multiple myeloma, or lithium toxicity. It may also result from laboratory error, so testing again and doctor evaluation are often needed to determine the cause.